

Skin treatments
PRP Hair Restoration by Doctors in Knightsbridge: Diagnosis First
Hair loss has many causes, and PRP only helps some of them. This doctor-led guide explains the main types of hair loss, how they are diagnosed, which blood tests matter, when PRP is appropriate, and how it fits with medical treatment.
 By Fatemeh, Founder & Lead Practitioner, Levirgo Aesthetics Clinic 18 min read
Reviewed September 2026

Why should a doctor diagnose hair loss before PRP?
Because PRP only helps certain types of hair loss. Pattern hair loss, stress-related shedding, autoimmune patches, scarring conditions and hair loss from iron deficiency or thyroid disease can look alike. A doctor identifies the cause, orders the right tests and treats it, so PRP is only used where it has a realistic chance of working.
Most people who come to a clinic asking for PRP have already decided that it is the answer. Sometimes it is. But a significant share of hair loss is driven by something PRP cannot fix: low iron stores, an underactive or overactive thyroid, a recent illness or childbirth, a new medicine, crash dieting, an autoimmune process, or inflammation that is permanently scarring the follicles. Treating those causes directly usually does far more than any injection.
The NHS describes normal shedding as between 50 and 100 hairs a day. It separates permanent causes, mainly male and female pattern hair loss that tends to run in families, from temporary causes such as illness, stress, weight loss, iron deficiency and cancer treatment. That distinction is the first thing a doctor wants to establish, because it decides whether the goal is to reverse a trigger, slow a lifelong process, or refer urgently.
A doctor-led approach also matters for safety. PRP involves a blood draw and multiple scalp injections, so bleeding disorders, anticoagulant medicines, fainting and infection risk all need to be considered. If the best plan includes prescription medicine, a doctor can counsel you on its risks and prescribe it, rather than leaving PRP to carry expectations it cannot meet.
What type of hair loss do you have?
The most common types are androgenetic alopecia (male or female pattern hair loss), telogen effluvium (diffuse shedding after a trigger), alopecia areata (autoimmune patches) and scarring alopecias. Traction and medical causes such as iron deficiency or thyroid disease are also common. Each has a different outlook and treatment.
| Type | What it usually looks like | Typical cause or trigger | Role of PRP |
|---|---|---|---|
| Male pattern hair loss (androgenetic alopecia) | Receding temples, thinning crown | Genetic sensitivity of follicles to DHT | Reasonable add-on in early to moderate loss |
| Female pattern hair loss | Widening central part, diffuse crown thinning, hairline kept | Genetic and hormonal factors; sometimes PCOS | Reasonable add-on in early to moderate loss |
| Acute telogen effluvium | Sudden diffuse shedding, full-length hairs | Fever, childbirth, surgery, weight loss, some medicines | Rarely needed; treat the trigger and allow recovery |
| Chronic telogen effluvium | Long-running shedding with good overall density | Often unclear; iron and thyroid checked | Only after causes are addressed, case by case |
| Alopecia areata | Smooth, round patches; sometimes nail pitting | Autoimmune | Occasionally used under medical care; steroid injection is standard |
| Scarring (cicatricial) alopecia | Shiny patches with loss of follicle openings, itch or burning | Inflammatory conditions such as frontal fibrosing alopecia | Not a primary treatment; urgent specialist referral |
| Traction alopecia | Thinning at the hairline or where hair is pulled | Tight hairstyles, extensions | Stop the traction first; PRP may be considered later |
Descriptions drawn from the Primary Care Dermatology Society (PCDS) alopecia guidance and British Association of Dermatologists patient leaflets. Diagnosis requires examination.
Androgenetic alopecia: the main PRP candidate
In both men and women, pattern hair loss happens when affected follicles gradually miniaturise: each new hair is finer, shorter and lighter until the follicle stops producing visible hair. The British Association of Dermatologists notes that over 190 genes have been linked to male pattern hair loss. Because miniaturised follicles are still alive for a long time, this is the window in which PRP and medical treatment can help.
Telogen effluvium: shedding with a cause
Telogen effluvium happens when a shock pushes many growing hairs into the resting phase at once. PCDS guidance describes shedding typically starting two to three months after a trigger such as high fever, childbirth, surgery or significant weight loss, and recovering within three to six months if the trigger resolves. Chronic telogen effluvium mainly affects middle-aged women, who may notice heavy shedding while still having good density for their age.
Alopecia areata and scarring alopecia
Alopecia areata is autoimmune. PCDS guidance cites a study in which 80% of people with a small number of patches regrew within a year without treatment, whereas fewer than 10% of people with total scalp or body hair loss made a full recovery. Scarring alopecias are different again: they destroy follicles permanently, so PCDS advises urgent specialist referral to limit irreversible loss.
What happens at a doctor-led hair loss assessment?
A doctor-led assessment combines a detailed history, scalp examination with dermoscopy (trichoscopy), a hair pull test, standardised photographs and targeted blood tests. Together these identify the type of hair loss, any treatable cause and whether PRP, medical treatment, both or a specialist referral is the right next step.
- History
When it started, whether it is shedding or thinning, family history, recent illness, childbirth, surgery, weight change, diet, stress, new medicines, hair care and styling, and symptoms such as itch, burning, irregular periods, acne or excess body hair.
- Scalp examination and trichoscopy
A magnified look at the scalp shows whether follicle openings are preserved, how many hairs are miniaturised, and signs of inflammation or scarring. The pattern is graded on recognised male or female scales.
- Pull test and photographs
A gentle pull test shows whether shedding is active. Standardised photographs of the part, crown and hairline create a baseline for fair comparison later.
- Blood tests where indicated
Baseline tests for diffuse hair loss, plus targeted tests if the history suggests a hormonal, nutritional or autoimmune cause.
- Diagnosis and plan
You leave with a clear explanation of the likely diagnosis, the options with their evidence and risks, and what success would realistically look like. If PRP is not appropriate, you are told so.
- Referral when needed
Suspected scarring alopecia, extensive alopecia areata or an unclear diagnosis may need a consultant dermatologist and sometimes a scalp biopsy.
This is also where the difference between a doctor and a non-medical hair practitioner shows. A doctor can examine, order and interpret blood tests, prescribe, manage side effects, and refer within the medical system. At Levirgo, related needs can be handled through our dermatology consultation, private GP appointments and prescription service, alongside PRP therapy when it is appropriate.
Which blood tests are used to investigate hair loss?
For diffuse hair loss, PCDS guidance recommends a full blood count, ferritin (iron stores) and thyroid function tests as a baseline. Kidney and liver function, zinc and vitamin D may be added depending on the history, and women with signs of excess androgens, such as acne, excess hair or irregular periods, need further hormonal investigation.
| Test | Why it is checked | When it is used |
|---|---|---|
| Full blood count (FBC) | Anaemia and other blood abnormalities | Baseline for diffuse hair loss |
| Ferritin | Iron stores, a common and treatable contributor to shedding | Baseline for diffuse hair loss |
| Thyroid function tests (TFT) | Under- or overactive thyroid disrupts the hair cycle | Baseline for diffuse hair loss |
| Vitamin D and zinc | Nutritional contributors | Depending on history and diet |
| Kidney (U&E) and liver function | General health and medicine safety | Depending on history and planned treatment |
| Hormone tests | Excess androgens, for example in polycystic ovary syndrome | Women with acne, excess hair or irregular periods |
Source: Primary Care Dermatology Society, Alopecia: an overview (FBC, ferritin and TFT as baseline; U&E, LFT, zinc and vitamin D depending on presentation; further tests with clinical hyperandrogenism). Tests are chosen individually, not as a routine panel for everyone.
Bring your history with you
If you have had blood tests in the last few months, bring the results. Also note any illness, operation, pregnancy, diet change or new medicine in the six months before the shedding started. That timeline is often the single most useful piece of information in diagnosing telogen effluvium.
Hormonal causes deserve a special mention for women. Female pattern hair loss can accompany polycystic ovary syndrome, and the British Association of Dermatologists lists PCOS among its associations. If irregular periods, acne or excess facial hair are part of the picture, the hair loss is best managed as part of a wider plan, such as our approach to PCOS treatment in Knightsbridge.
When is PRP appropriate for hair loss, and when is it not?
PRP is most appropriate for early to moderate androgenetic alopecia in men and women who still have miniaturised hairs, ideally alongside medical treatment. It is not appropriate for scarring alopecia, a smooth bald scalp, untreated iron or thyroid problems, active scalp infection, or people with bleeding or platelet disorders.
| Clinical situation | PRP decision | Why |
|---|---|---|
| Early to moderate pattern loss, miniaturised hairs present | Reasonable, usually with medical treatment | Best-studied indication; follicles still active |
| Pattern loss, cannot take or declines medication | Reasonable as a stand-alone option | Trials show benefit over placebo, with realistic expectations |
| Acute telogen effluvium with a clear trigger | Usually not | Often recovers within 3 to 6 months once the trigger resolves |
| Low ferritin or abnormal thyroid tests | Not yet | Correct the cause first, then reassess |
| Patchy alopecia areata | Case by case, under medical care | Steroid injection is standard; PRP evidence is smaller |
| Scarring alopecia | No | Needs urgent specialist treatment to stop permanent loss |
| Advanced loss, smooth scalp, no fine hairs | No | No active follicles to stimulate; transplant assessment instead |
| Bleeding or platelet disorder, active scalp infection | No | Safety |
General guidance based on PCDS and BAD guidance and the systematic reviews cited below. Individual decisions are made in consultation.
Do not delay if you notice these
Itching, burning, pain or redness of the scalp, shiny patches where follicle openings seem to have disappeared, or a hairline that is receding along with eyebrow loss can indicate a scarring alopecia. PCDS guidance describes these conditions as irreversible and advises urgent referral. Book a medical assessment rather than a cosmetic course.
There is an honest middle ground too. Some people have mild pattern loss plus a second factor, such as borderline iron stores or a stressful year. A sensible plan may correct the second factor first, start medical treatment, and add PRP three to six months later if the response is not enough. That staged approach costs less and makes it easier to tell what is actually working.
What does the evidence show for PRP in different types of hair loss?
The evidence is strongest in androgenetic alopecia: a 2024 meta-analysis found about 27.55 more hairs/cm² with PRP than placebo, though trials were heterogeneous. In women, PRP increased terminal hair density. In alopecia areata, a 2022 meta-analysis found no significant difference between PRP and steroid injections, with more trials needed.
Pattern hair loss. Kieling and colleagues pooled randomised trials in 2024 and found a mean increase in hair density of 27.55 hairs/cm² with PRP compared with placebo. They also judged the studies to be highly heterogeneous, of low quality and affected by publication bias, and called for better trials. An earlier 2023 meta-analysis of nine trials by Zhang and colleagues found PRP increased hair density at three and six months compared with placebo, with no serious adverse reactions.
Women. A 2023 meta-analysis focused on female pattern hair loss (de Oliveira and colleagues) found PRP-based treatment increased terminal hair density compared with control, without a significant change in hair thickness, and no major side effects. The authors advised caution until results are replicated in larger samples.
Alopecia areata. The first randomised half-head study, by Trink and colleagues in the British Journal of Dermatology in 2013, reported more regrowth with PRP than with steroid injection or placebo in 45 patients. Later pooled analysis (Meznerics and colleagues, 2022) found no significant difference between PRP and triamcinolone steroid injections. PRP may therefore be an option for people who respond poorly to, or cannot tolerate, steroid injections, under medical supervision.
What dermatology bodies say. UK guidance is deliberately cautious. PCDS describes PRP as safe but says more evidence is needed. The British Association of Dermatologists says research suggests some benefit that is unpredictable, and that PRP is not offered on the NHS. A doctor-led clinic should present PRP in exactly those terms.
Although safe, more evidence is needed.
Primary Care Dermatology Society, on PRP for male and female pattern alopecia
Find out what is causing your hair loss
Book a doctor-led assessment in Knightsbridge. We examine your scalp, arrange the right tests and tell you honestly whether PRP is worth doing.
How does PRP combine with medical treatment for hair loss?
For pattern hair loss, medical treatment is the foundation and PRP is an add-on. PCDS guidance estimates topical minoxidil benefits about 40% of patients and 5-alpha reductase inhibitors up to 90% of men. Adding PRP to minoxidil improved hair density further in a 2024 meta-analysis, although the certainty of that evidence was low.
| Treatment | Who it is for | What the guidance says | Key cautions |
|---|---|---|---|
| Topical minoxidil 5% | Men and women | Benefits an estimated 40%; best results at 6 to 12 months (PCDS) | Initial shedding, scalp irritation; must be continued |
| Low-dose oral minoxidil | Men and women, prescribed | Starts at 0.25 mg daily, increased to 1 mg (PCDS) | Excess body or facial hair reported in 14% |
| Finasteride or dutasteride | Men, prescribed | Up to 90% may benefit (PCDS); up to 14 months to see benefit (BAD) | MHRA warnings on depression, suicidal thoughts and sexual dysfunction |
| Anti-androgen medicines | Selected women, prescribed | Options such as spironolactone listed by BAD | Not in pregnancy; monitoring may be needed |
Sources: PCDS, Male and female pattern alopecia; BAD patient leaflets; MHRA Drug Safety Update, May 2026. Prescription-only medicines require a consultation and are not suitable for everyone.
Finasteride and minoxidil: British Association of Dermatologists, male pattern hair loss leaflet. Telogen effluvium recovery after the trigger resolves: PCDS. PRP: improvement most commonly reported after the third month (Stevens and Khetarpal, 2018). Bars show the longest point in each range.
Why combine? The medicines act on the underlying hormonal drive (finasteride and dutasteride) or on follicle growth (minoxidil), and they only work for as long as they are used, as the NHS notes. PRP is thought to support the follicles through growth factors. In a 2024 meta-analysis of five randomised trials by Yao and colleagues, adding PRP to topical minoxidil produced significantly higher hair density at one, three and five to six months than minoxidil alone, with a similar rate of adverse events. The authors graded the certainty of that evidence as low to very low, which is a fair summary of the whole field.
Finasteride needs a proper medical conversation
In May 2026 the MHRA updated its safety advice on finasteride and dutasteride. Prescribers are asked to check for any history of depression or suicidal thoughts before prescribing, and patients are advised to stop finasteride 1 mg immediately and seek help if they develop depression or suicidal thoughts, and to tell their doctor about sexual side effects. Patient cards are provided in packs. This is one reason hair loss medicine should be prescribed after a consultation rather than bought as an add-on.
How is doctor-led PRP for hair performed safely?
Safe PRP for hair starts with screening for bleeding disorders, anticoagulants, infection and fainting risk, then uses single-use sealed kits, sterile technique and a documented preparation. Common after-effects are scalp tenderness, tightness and a mild headache for a day or two; serious complications are rare in published trials.
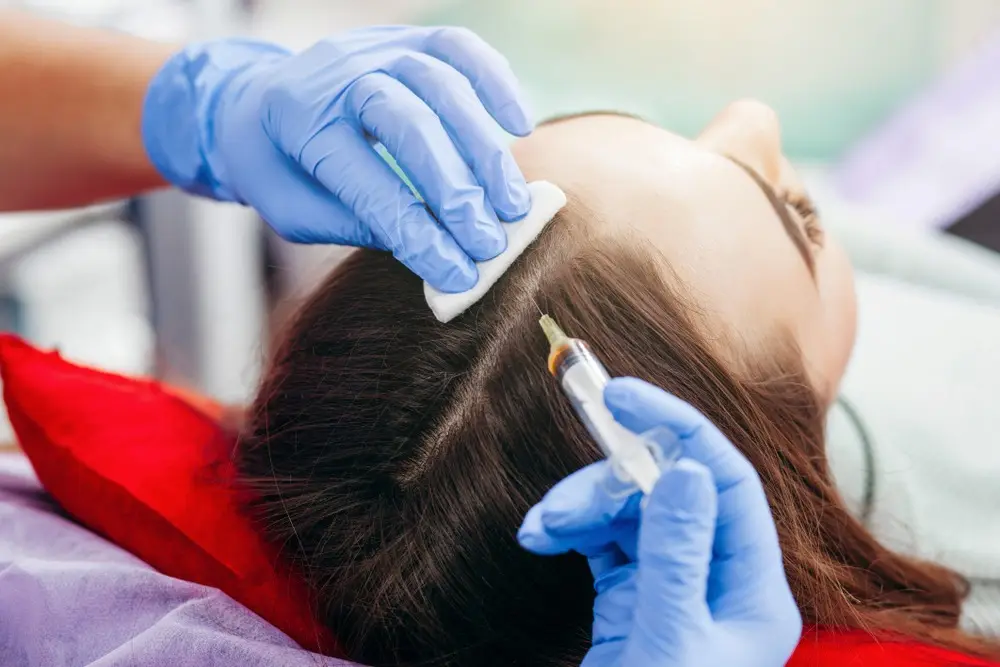
- Medical screening: platelet or bleeding disorders, anticoagulant and antiplatelet medicines, active cancer or chemotherapy, pregnancy and breastfeeding, active scalp infection or inflammation, and a history of fainting with needles.
- Preparation: a sealed, single-use kit with a known protocol. A 2018 protocol review recommended platelet enrichment of 3 to 6 times whole blood.
- Comfort: cooling, vibration or local anaesthetic techniques reduce injection discomfort.
- After-effects: tenderness, tightness, pinpoint bleeding, mild swelling that can track to the forehead, and occasionally a headache, usually settling within 24 to 48 hours.
- Trial safety: the Gentile 2015 half-head trial reported no side effects during treatment, and a 2023 meta-analysis reported no serious adverse reactions.
Consent is part of safety. GMC guidance for doctors who offer cosmetic interventions says the doctor performing a procedure should seek consent personally, discuss likely outcomes, benefits and risks clearly, and give patients time to reflect. For hair loss, that includes being explicit that PRP needs maintenance and that results in trials vary widely between people.
How much does doctor-led hair loss assessment and PRP cost in London?
In London, a doctor-led hair loss consultation typically costs £100 to £300, with blood tests priced by panel. PRP for hair is usually £300 to £650 per session, and a course of three to four sessions £800 to £2,200. Prescription medicines, if suitable, are an additional ongoing cost.
| Component | Typical London price | Notes |
|---|---|---|
| Doctor-led hair loss consultation | £100 to £300 | Often includes trichoscopy and photographs; sometimes redeemable |
| Blood tests | Varies by panel | Chosen according to history; not everyone needs the same tests |
| Single PRP session (scalp) | £300 to £650 | Depends on preparation system and area |
| Course of 3 PRP sessions | £800 to £1,700 | Usually about a month apart |
| Course of 4 PRP sessions | £1,000 to £2,200 | Sometimes chosen for more extensive thinning |
| Maintenance PRP session | £300 to £600 | Commonly every 4 to 6 months |
Indicative ranges for London clinics, not Levirgo prices. PRP for hair loss is not offered on the NHS (British Association of Dermatologists). Your plan and price are confirmed in writing after assessment.
The most expensive plan is the one aimed at the wrong diagnosis. Spending on a diagnostic consultation and appropriate blood tests first can prevent a full PRP course for shedding that would have recovered on its own, or for an iron deficiency that a few months of treatment would have corrected.
How do you choose a hair loss doctor in London?
Choose a GMC-registered doctor who examines your scalp in person, orders and interprets blood tests, discusses medical and procedural options with their evidence, and refers to a consultant dermatologist when needed. Ask whether the clinic is CQC-registered and how PRP is prepared, and avoid anyone who recommends PRP before making a diagnosis.
- Registration: check the doctor on the General Medical Council register. Nurses performing PRP should be on the Nursing and Midwifery Council register.
- Diagnosis before sales: a named diagnosis, and a written explanation of why PRP is or is not recommended.
- Evidence-based options: medical treatment discussed alongside PRP, with honest effect sizes and timelines.
- Regulation: the Government’s 2023 consultation on licensing non-surgical cosmetic procedures in England proposed placing cosmetic PRP in its amber, medium-risk tier, so training and oversight should be clear.
- Follow-up: baseline photographs, a review at a set point such as three or six months, and a plan for maintenance or stopping.
- Referral pathways: access to a consultant dermatologist for scarring alopecia or extensive alopecia areata, and to a surgeon for transplant assessment in advanced loss.
Why see Levirgo’s doctors in Knightsbridge for hair loss?
Levirgo is a doctor-led clinic at 6 Beauchamp Place, Knightsbridge, SW3 1NG, near Harrods and a few minutes’ walk from Knightsbridge Underground station on the Piccadilly line. Aesthetic treatments and private GP care sit under one roof, so diagnosis, blood tests, prescribing and PRP can form a single plan.
Our starting point is always the cause. We take a full history, examine the scalp, arrange appropriate tests, and explain the likely diagnosis before discussing any treatment. When PRP is a sensible option, it is combined with evidence-based medical care where suitable and reviewed against baseline photographs. When it is not, we say so and suggest what would help instead, including referral.
Patients regularly travel from nearby neighbourhoods. The clinic is a short walk from Belgravia, a few minutes from Chelsea, and within easy reach of Kensington and Mayfair. You can book a consultation online or send us a question first. For the wider range of options, browse our skin treatments.
Frequently asked questions
Do I need blood tests before PRP for hair loss?
Often, yes. For diffuse hair loss, Primary Care Dermatology Society guidance recommends a full blood count, ferritin and thyroid function tests as a baseline, with vitamin D, zinc, kidney and liver tests or hormone tests added depending on your history. People with classic male pattern hair loss and no other symptoms may not need them. Your doctor will explain which tests are relevant and why.
How do I know if my hair loss is genetic or caused by something else?
Pattern hair loss develops gradually in a typical pattern, often with a family history, and shows miniaturised hairs on trichoscopy. Telogen effluvium usually starts suddenly two to three months after a trigger such as illness or childbirth. Patches suggest alopecia areata, and itching, burning or shiny skin can suggest scarring alopecia. An examination is needed to tell them apart reliably.
Does PRP work for female hair loss?
It can help female pattern hair loss. A 2023 meta-analysis found PRP increased terminal hair density compared with control, without a significant change in hair thickness and without major side effects. The authors advised caution until larger trials confirm the results. Iron, thyroid and hormonal causes should be checked first, and PRP usually works best alongside medical treatment.
Can PRP help telogen effluvium?
PRP is rarely the first step. Acute telogen effluvium usually recovers within three to six months once the trigger resolves, according to PCDS guidance, so the priority is identifying and correcting that trigger, such as low iron. Chronic telogen effluvium may occasionally be considered for PRP after causes are addressed, but the evidence is much stronger for pattern hair loss.
Is PRP effective for alopecia areata?
It may be. A 2013 randomised half-head study found more regrowth with PRP than steroid injection or placebo, and a 2022 meta-analysis found no significant difference between PRP and steroid injections. Steroid injection remains standard, and many small patches regrow without treatment. PRP may suit people who respond poorly to or cannot tolerate steroids, under medical supervision.
Should I take finasteride or minoxidil as well as PRP?
For pattern hair loss, medical treatment is the foundation and PRP is an add-on. PCDS guidance estimates topical minoxidil benefits about 40% of patients and 5-alpha reductase inhibitors up to 90% of men. Finasteride carries MHRA warnings about mood and sexual side effects, so it should only be started after a proper consultation. A doctor will help you weigh the options.
Why is it better to have PRP with a doctor?
A doctor can diagnose the cause of hair loss, order and interpret blood tests, prescribe and monitor medicines, manage bleeding risks and complications, and refer to a dermatologist when needed. That reduces the chance of spending money on PRP for a type of hair loss it cannot help, and makes it more likely PRP is combined with treatments that work.
Who should not have PRP for hair?
PRP is not suitable for scarring alopecia as a primary treatment, a completely smooth bald scalp, active scalp infection, platelet or bleeding disorders, or during pregnancy and breastfeeding. Anticoagulant medicines, active cancer or chemotherapy and uncontrolled medical conditions need a doctor’s review. Untreated iron deficiency or thyroid disease should be corrected before considering PRP.
How much does a hair loss consultation cost in London?
A doctor-led hair loss consultation in London typically costs £100 to £300, sometimes redeemable against treatment. Blood tests are priced according to the tests needed. PRP sessions are usually £300 to £650 each, and courses of three to four sessions £800 to £2,200. These are indicative ranges, confirmed in writing after assessment.
Is hair loss from PCOS treatable with PRP?
Female pattern hair loss can accompany polycystic ovary syndrome. Managing the hormonal picture is usually the priority, sometimes with anti-androgen medicines prescribed after assessment, alongside topical treatment. PRP can be considered as an add-on for thinning once the wider plan is in place. A joined-up approach to PCOS tends to help skin, hair and cycle symptoms together.
When should I see a doctor urgently about hair loss?
Seek prompt medical advice if hair loss comes with scalp pain, burning, itching, redness or scaling, shiny patches, eyebrow loss with a receding hairline, sudden extensive shedding, or signs of illness such as weight loss or fatigue. Scarring alopecias cause permanent loss, and PCDS guidance advises urgent specialist referral when they are suspected.
How long before I know whether treatment is working?
Be patient. The British Association of Dermatologists advises using minoxidil for at least 6 and possibly 12 months, and finasteride can take up to 14 months to show benefit. PRP improvements are most often reported after the third month. Standardised photographs at baseline and at a planned review give the fairest answer.
Levirgo Aesthetics Clinic · Knightsbridge
A diagnosis first, then the right treatment
Doctor-led hair loss assessment, targeted blood tests, evidence-based medical options and PRP only where it makes sense. No obligation to proceed.
Sources & further reading
- NHS. Hair loss
- Primary Care Dermatology Society. Alopecia: an overview
- Primary Care Dermatology Society. Male pattern alopecia (androgenetic alopecia) and female pattern alopecia
- Primary Care Dermatology Society. Alopecia areata
- British Association of Dermatologists. Hair loss, male pattern (androgenetic alopecia): patient information leaflet
- British Association of Dermatologists. Hair loss, female pattern (androgenetic alopecia): patient information leaflet
- MHRA Drug Safety Update. Finasteride and dutasteride: updated safety warnings for psychiatric side effects and sexual dysfunction, May 2026
- Gan DC, Sinclair RD. Prevalence of male and female pattern hair loss in Maryborough. J Investig Dermatol Symp Proc, 2005
- Kieling L et al. Is autologous PRP capable of increasing hair density in androgenic alopecia? Systematic review and meta-analysis. An Bras Dermatol, 2024
- de Oliveira AFQ et al. Use of autologous platelet-rich plasma in androgenetic alopecia in women: systematic review and meta-analysis. J Dermatolog Treat, 2023
- Meznerics FA et al. Platelet-Rich Plasma in Alopecia Areata: systematic review and meta-analysis of randomized clinical trials. Biomedicines, 2022
- Yao J et al. The additive value of PRP to topical minoxidil in androgenetic alopecia: systematic review and meta-analysis. PLoS One, 2024
- Trink A et al. A randomized, double-blind, placebo- and active-controlled, half-head study of PRP on alopecia areata. Br J Dermatol, 2013
This article is general information about hair loss and PRP treatment and is not medical advice. The evidence for PRP is still developing and individual results vary. Diagnosis, tests and suitability for any treatment, including prescription medicines, can only be established in a personal consultation. Prices are indicative London ranges for 2026, are not Levirgo prices, and are confirmed in writing after assessment.