

Skin treatments
Skin Tag and Blemish Removal in Knightsbridge: Methods Compared
Skin tags, seborrhoeic keratoses, cherry angiomas and milia are harmless, but they catch on clothing, bleed and bother people. This guide compares the ways they can be removed, what the evidence says about results and scarring, and why every lesion should be assessed before anyone treats it.
 By Fatemeh, Founder & Lead Practitioner, Levirgo Aesthetics Clinic 19 min read
Reviewed September 2026

What are skin tags and benign skin blemishes?
Skin tags are soft, skin-coloured growths that hang from the skin, usually in folds such as the neck, armpits and eyelids. Other common benign blemishes include seborrhoeic keratoses (stuck-on warty spots), cherry angiomas (red blood spots), milia (tiny white cysts) and dermatofibromas.
None of these lesions are cancerous and none become skin cancer, but they are easily confused with each other and, occasionally, with something that does need medical attention. Knowing what you have is the first step to choosing whether and how to remove it.
| Lesion | What it looks like | Where it appears | Usual removal options |
|---|---|---|---|
| Skin tag | Soft, skin-coloured or slightly darker, on a stalk; 2mm to 5cm | Neck, armpits, eyelids, under breasts, groin | Snip excision, cautery, cryotherapy |
| Seborrhoeic keratosis | Rough, “stuck-on”, pink to almost black | Trunk, head and neck | Cryotherapy, curettage, laser |
| Cherry angioma | Bright red to purple dome; black if thrombosed | Trunk most commonly | Electrocautery, laser, curettage |
| Milia | Tiny white, firm cysts | Around eyes and cheeks | De-roofing and expression, careful cautery |
| Dermatosis papulosa nigra | Many small dark brown or black bumps, a form of seborrhoeic keratosis | Face and neck in darker skin | Often left alone; any treatment carries pigment risk |
| Dermatofibroma | Small rubbery button that may dimple when gently squeezed | Lower legs most often; upper arms in women | Usually best left; excision scar is often more noticeable |
Descriptions from NHS skin tags guidance, British Association of Dermatologists seborrhoeic keratosis leaflet and Primary Care Dermatology Society chapters on angiomas and milia. Dermatofibroma details from the BAD dermatofibroma leaflet.
The NHS notes that skin tags can be confused with warts and moles. Warts are usually firm and rough, and most common on the hands and feet; for plantar warts, see our verruca freeze treatment. Moles are usually flat, round or oval and a different colour from the surrounding skin. A pigmented mole is a different conversation, and our single mole check guide explains why moles are handled more cautiously.
How common are skin tags and seborrhoeic keratoses?
Very common. A study of 750 unselected people found 46% had skin tags, rising with age. The British Association of Dermatologists reports that 30% of people have a seborrhoeic keratosis by 40 and 75% by 70. Skin tags are also more likely with obesity, type 2 diabetes and pregnancy.
Skin tags often grow where skin rubs against skin. The NHS says you may be more likely to develop them if you are living with obesity or have skin folds that rub, if you have type 2 diabetes (severe insulin resistance is thought to encourage them), or during pregnancy because of hormonal changes. If you have noticed a sudden crop of many new skin tags, it is reasonable to mention it to your GP, who may consider checking your blood sugar.
Seborrhoeic keratoses are just as common, and because many are brown or black, they are frequently mistaken for moles.
Seborrhoeic keratoses have no link to viral warts or oil glands despite their old name, “seborrhoeic warts”. The BAD says their cause is unknown, sunlight may play a part, and some people inherit a tendency to develop many. They are not infectious and do not become cancer, but once present they usually stay and new ones may appear over the years.
Why does every lesion need assessing before removal?
Because appearances deceive. The BAD warns that a very dark seborrhoeic keratosis can look like melanoma, a thrombosed angioma can suddenly turn black, and some skin cancers present as pink or pearly bumps. A clinician should confirm a lesion is benign, ideally with dermoscopy, before any destructive removal.
Get a medical assessment first if a lesion
is new and pigmented, or is changing in size, shape or colour; bleeds without being caught or injured; is a sore or scab that does not heal or keeps coming back; is a shiny, pearly or pink lump that is growing; is crusty, scaly or painful and getting bigger; or looks different from your other spots. The NHS also advises seeing a GP about a skin tag that gets bigger, becomes painful, starts bleeding or develops into lots of skin tags. These are not reasons to panic, but they are reasons to have a diagnosis before cosmetic treatment.
Cancer Research UK describes non-melanoma skin cancers as a new or changing spot, lump or growth, sometimes shiny, red, pink or pearly white, and on brown or black skin more likely to look pearly, brown or black; a sore that does not heal; or a red or dark patch that may be crusty or scaly. Several of those descriptions could be mistaken for a “blemish” by someone who has not been trained to tell the difference.
This is also why the method matters. Freezing, burning and laser destroy tissue, so if the lesion was not what it seemed, the chance to examine it under a microscope is gone. The British Association of Dermatologists advises against removing moles by laser for exactly this reason. Where there is any doubt, the right options are to remove the lesion in a way that allows histology, to photograph and review it, or to refer. If you have many lesions and want them all looked at, a full body mole and blemish check is a sensible starting point.
Can you get skin tags removed on the NHS?
Usually not. The NHS says skin tag removal is considered cosmetic, and NHS Evidence-Based Interventions guidance restricts removal of benign lesions to set criteria, such as regular bleeding, repeated infection, pain needing daily medication, or blocked vision. Any lesion suspicious of cancer is referred under NICE guidelines.
The Evidence-Based Interventions programme, developed for NHS England by the Academy of Medical Royal Colleges, lists benign lesions including skin tags, seborrhoeic keratoses, milia, benign moles, dermatofibromas and xanthelasmata. It explains that treatment carries a risk of infection, bleeding or permanent scarring, so it is not usually offered just to improve appearance. A lesion must meet at least one criterion to be considered for NHS removal.
| Criterion | What the guidance specifies |
|---|---|
| Trauma and bleeding | Unavoidably traumatised with bleeding more than twice weekly for at least 4 weeks in everyday activities, not from picking |
| Infection | Repeated infection needing 2 or more antibiotic courses a year |
| Pain | Pain requiring long-term daily medication |
| Obstruction | Obstructing an orifice or impairing field of vision |
| Function | Significantly restricting function, such as joint movement |
| Pressure | Unavoidable pressure symptoms that cannot be managed conservatively |
Source: Evidence-Based Interventions, Removal of benign skin lesions (Academy of Medical Royal Colleges, last reviewed September 2024). Local NHS commissioners may apply their own versions of these criteria.
For everyone else, removal is a private, self-funded procedure. That makes it doubly important to choose a provider who assesses first and who would refer you to the NHS if a lesion turned out to be suspicious.
What are the main removal methods?
The main methods are snip excision with fine scissors, electrocautery (heat), cryotherapy (freezing with liquid nitrogen), curettage or shave (scraping or slicing off), and laser. The NHS lists heat, freezing and cutting for skin tags; the BAD lists freezing, laser and curettage for seborrhoeic keratoses.
| Method | Best suited to | Sample for histology? | Main trade-offs |
|---|---|---|---|
| Snip excision | Stalked skin tags | Yes | Brief sting; tiny bleed; very small mark |
| Electrocautery or hyfrecation | Small tags, cherry angiomas, milia, papules | No | Small scab; risk of pale or dark marks |
| Cryotherapy | Seborrhoeic keratoses, some small tags | No | Blistering and scab; pigment loss, especially on darker skin |
| Curettage or shave | Thicker seborrhoeic keratoses, bleeding angiomas | Yes | Needs local anaesthetic; shallow wound heals over weeks |
| Laser | Selected angiomas and flat pigmented keratoses | No | Cost; redness and pigment change; not for moles |
| Excision with stitches | Anything uncertain, or larger lesions | Yes, whole lesion | Line scar; stitches out in 7 to 14 days |
Methods from NHS skin tags guidance, the British Association of Dermatologists seborrhoeic keratosis and cryotherapy leaflets, and Primary Care Dermatology Society guidance, which recommends curettage with histology for angiomas that catch or bleed.
Why one method does not suit every lesion
A skin tag hangs from a narrow stalk, so snipping it at the base is quick and leaves very little behind. A seborrhoeic keratosis sits on the skin surface like a crust, so freezing or gently scraping it off works well. A cherry angioma is a cluster of blood vessels, which heat or vascular laser can seal. Milia are tiny keratin cysts just under the surface; the Primary Care Dermatology Society notes that in adults the surface can be broken with a sterile needle or blade and the contents expressed, and careful cryotherapy or diathermy can also work. Treating each lesion with a method matched to its structure gives a better result with less damage to the surrounding skin.
Which removal method works best? What the evidence says
For stalked skin tags, a 2025 randomised trial of 1,257 skin tags found scissor snip excision healed 85% at 12 weeks versus 71% with a 532nm laser, with less pain. A 2024 trial found electrosurgery outperformed cryotherapy for skin tags and angiomas, while cryotherapy did better for seborrhoeic keratoses.
Good-quality trials of cosmetic lesion removal are surprisingly rare, but two recent randomised studies are useful. In a German trial published in Archives of Dermatological Research, 68 patients with 1,257 skin tags on the neck or armpits had one side treated by scissor snip excision and the other by a non-ablative 532nm laser, with an observer blinded to the method.
Source: Haase et al., Arch Dermatol Res 2025; randomised, intra-individual, observer-blinded trial of 68 patients and 1,257 skin tags. Response is the adjusted overall response rate. 18% of patients had no preference.
The laser was about 39% faster and bloodless, but it caused more redness and more hyper- and hypopigmentation, and treated tags could persist as dead tissue for up to three weeks. Mean pain scores were lower for snip excision (2.6 versus 3.42). The authors concluded that scissor snip excision remains the gold standard for stalked skin tags.
A second, smaller assessor-blinded randomised trial from Iran compared cryotherapy and electrosurgery across four lesion types, with 32 lesions in each group. Patient and physician satisfaction was significantly higher with electrosurgery for skin tags, cherry angiomas and sebaceous hyperplasia, while seborrhoeic keratoses responded better to cryotherapy. Side effects were uncommon in both groups: hypopigmentation or depigmentation after cryotherapy, and hypopigmentation or small atrophic scars after electrosurgery, each in a few per cent of cases.
What this means in practice
There is no single best method. Snip excision tends to suit stalked skin tags, heat suits small vascular spots, and freezing or curettage suits seborrhoeic keratoses. Ask your clinician why they are recommending a particular method for your lesion, and what the likely mark will look like on your skin tone.
What happens at a skin tag or blemish removal appointment?
You discuss which lesions bother you and why, the clinician examines each one, often with a dermatoscope, confirms it is benign and suitable, explains the method and likely mark, and gains your consent. Most small lesions take minutes to treat, sometimes after a little local anaesthetic, and you go straight home.
- Consultation
Which lesions you want treated, how long you have had them, whether they have changed, bled or become sore, your medical history, any tendency to raised or keloid scars, and medicines such as blood thinners.
- Assessment of each lesion
Each lesion is examined in good light, with dermoscopy where useful. Anything that is not clearly benign is not treated cosmetically; it is sampled for histology, reviewed, or referred.
- Plan and consent
The method for each lesion, the likely mark, the healing time and the risk of pigment change are explained, so you can decide with realistic expectations.
- Treatment
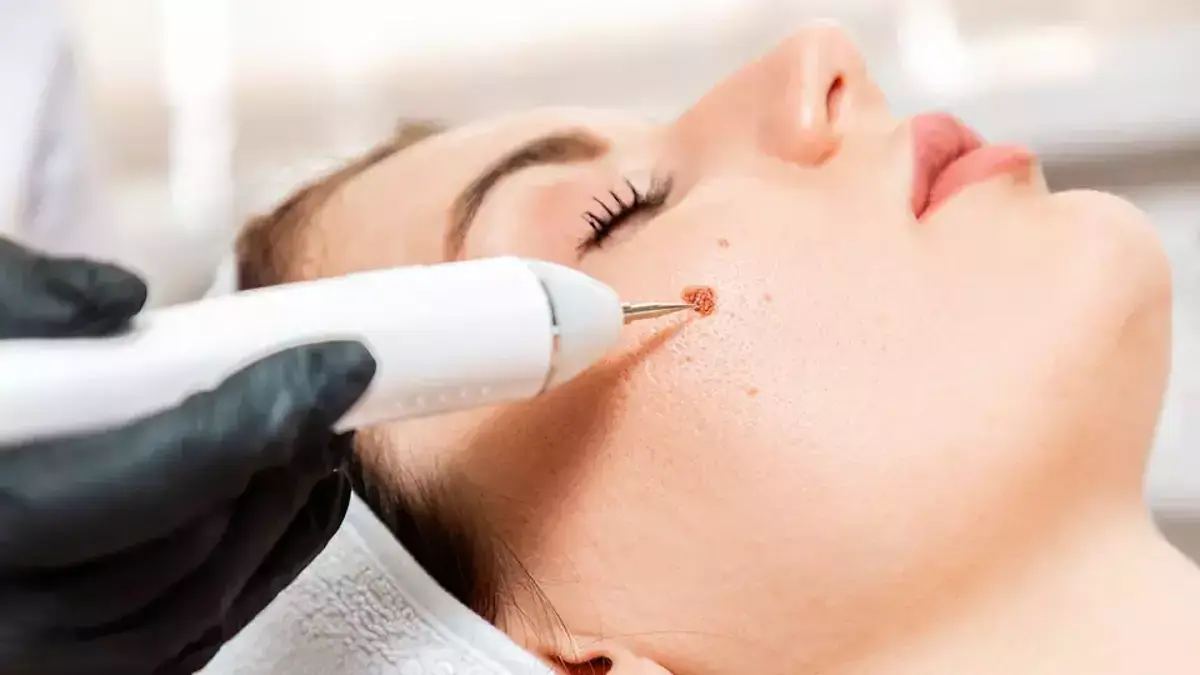
The skin is cleaned, local anaesthetic is used where needed, and the lesion is removed. Snipping and cautery take seconds to minutes; cryotherapy involves a freeze of a few seconds and a short thaw.
- Aftercare
You receive written wound care instructions and know who to contact if you have any concerns while the area heals.
Arrive without make-up or fake tan on the treatment areas. Tell the clinician if you are pregnant or taking blood-thinning medicines, and mention any history of raised or keloid scars.
Bothered by skin tags or blemishes?
Have each lesion assessed first, then removed with the method best suited to it and your skin.
How long does healing take after blemish removal?
Most small removals leave a small scab that falls off within 1 to 3 weeks. After cryotherapy, redness and swelling usually settle in 2 to 3 days and the scab can take a few weeks, longer on the legs. Pink or pale marks then fade gradually. There is little or no time off work.
| Timeframe | Snip excision or cautery | Cryotherapy |
|---|---|---|
| Same day | Tiny wound or crust; mild sting | White frozen area thaws in 1 to 2 minutes; redness and swelling |
| Days 1 to 3 | Small scab forms | Swelling settles; blister may form |
| Weeks 1 to 3 | Scab lifts off on its own | Scab forms and takes a few weeks to fall off |
| Months 1 to 6 | Pink mark fades | Any lightening or darkening usually improves, but may persist |
Cryotherapy timings from the British Association of Dermatologists cryotherapy leaflet. Healing is slower on the lower legs and varies with lesion size and depth.
- Keep the area dry for about 24 hours, then wash gently and pat dry.
- A thin layer of petroleum jelly helps the area heal and limits crusting, as the BAD suggests after cryotherapy.
- Do not pick or scratch scabs, which increases the chance of scarring.
- Use a plaster only if clothing or jewellery will rub the area.
- Protect healing skin from the sun with clothing or a high-SPF sunscreen to reduce the risk of dark marks.
- Seek advice if you notice increasing pain, spreading redness, pus or fever, which can indicate infection.
Does skin tag removal leave a scar, and what are the risks?
Most small lesions heal with a barely visible mark, but any removal can leave a scar or pigment change. The NHS notes that removal can cause scarring or darker skin, particularly on black or brown skin, usually temporarily but sometimes permanently. Rarely, a raised or keloid scar forms.
Side effects are generally mild and short-lived, but it is worth knowing the full list before you decide. The British Association of Dermatologists cryotherapy leaflet describes pain, swelling and blistering as common immediate effects, with infection uncommon. Later effects can include a pale or white scar, lightening or darkening of the skin, temporary numbness if a superficial nerve is frozen, and, very rarely, a raised hypertrophic or keloid scar, which the BAD notes is more common in darker-skinned people.
| Side effect | How likely | How to reduce the risk |
|---|---|---|
| Pain or stinging | Common, brief | Local anaesthetic for snip or curettage; simple pain relief afterwards |
| Blistering (cryotherapy) | Common | Leave blisters intact unless advised otherwise |
| Infection | Uncommon | Keep clean; do not pick; seek advice if worsening |
| Lighter or darker marks | More likely on darker skin | Conservative settings, sun protection, choosing snip over freezing where suitable |
| Scar | Usually small; rarely raised or keloid | Mention any keloid history; avoid treating high-risk sites cosmetically |
| Regrowth or new lesions | Seborrhoeic keratoses can regrow; new ones may appear | Realistic expectations; retreatment if needed |
Sources: NHS skin tags guidance; British Association of Dermatologists cryotherapy and seborrhoeic keratosis leaflets. The NHS notes a removed skin tag does not usually return.
If you have ever developed a keloid, particularly on the chest, shoulders, upper back or earlobes, tell your clinician. Removing a small harmless tag from a keloid-prone site can occasionally leave a scar that is far more noticeable than the original lesion. Our guides to keloid injection and scar treatment explain how raised scars are managed.
Do not try home removal. The NHS advises against removing a skin tag yourself unless a GP recommends it, because of the risks of infection, bleeding and scarring. Tying off tags with thread, over-the-counter freezing kits and removal creams also bypass the assessment step entirely.
How much does skin tag and blemish removal cost in London?
In London, removing a first skin tag or small benign lesion typically costs about £90 to £350, with additional lesions at the same visit around £30 to £120 each. A lesion assessment is often £50 to £150, and histology, when needed, about £70 to £150 per sample. These are indicative ranges only.
| Item | Typical London range | Notes |
|---|---|---|
| Consultation and lesion assessment | £50 to £150 | Sometimes redeemable against treatment |
| First lesion removed | £90 to £350 | Depends on method, size and site |
| Each additional lesion, same visit | £30 to £120 | Multiple small tags may be priced as a group |
| Histology, when needed | £70 to £150 per sample | Recommended for anything uncertain |
Indicative London market ranges, not Levirgo’s price list. Your exact fee is confirmed in writing after assessment. The NHS may treat benign lesions that meet Evidence-Based Interventions criteria.
Price differences often reflect who is doing the assessment, whether dermoscopy and histology are available, and whether aftercare and review are included. The cheapest quote is rarely the best value if it skips the step that confirms a lesion is harmless.
How do you choose a clinic for skin tag and blemish removal?
Choose a clinic where a doctor or suitably trained clinician assesses every lesion before treatment, can send tissue for histology, offers more than one method so the technique fits the lesion, is candid about pigment and scar risk, and can refer you if something is not benign.
Regulation of lesion removal is more varied than many people assume. The Care Quality Commission regulates surgical procedures carried out by healthcare professionals, but its scope excludes curettage, cautery or cryocautery of warts, verrucae or other skin lesions carried out by a medical practitioner under local or no anaesthesia. In practice, that means you should ask about training and governance directly rather than assume every setting is inspected in the same way. A doctor’s registration can be checked on the GMC register.
- Will every lesion be assessed by a clinician, with dermoscopy, before treatment?
- Can tissue be sent for histology if there is any doubt?
- Which methods are available, and why is one recommended for my lesion?
- What will the mark look like on my skin tone, and how long will it take to fade?
- What happens if a lesion looks suspicious? There should be a clear referral route.
- Who handles aftercare if a wound becomes sore or infected?
Why choose Levirgo for skin tag and blemish removal in Knightsbridge?
Levirgo Aesthetics Clinic at 6 Beauchamp Place, Knightsbridge, SW3 1NG, close to Harrods and Knightsbridge Underground station, removes skin tags and benign blemishes using electrocautery, cryotherapy or laser, always after a thorough skin assessment to confirm a lesion is suitable and does not need dermatological referral.
Our starting point is the diagnosis, not the device. If a lesion is clearly benign, we recommend the method most likely to remove it cleanly with the smallest mark. If anything about it is uncertain, we say so, and we arrange a mole check, histology or referral rather than treating it cosmetically. Treatment takes place in a calm, private clinic with minimal downtime for most small lesions.

Beauchamp Place is a few minutes’ walk from Knightsbridge station on the Piccadilly line and convenient for patients from Kensington, South Kensington, Chelsea and Belgravia. You can book online or contact us with photos of the lesions you would like to discuss. See all our skin treatments.
Frequently asked questions
Does skin tag removal hurt?
Most people feel only a brief sting. Snip excision of a small tag is often done with or without a little local anaesthetic, cautery can be done after numbing, and cryotherapy causes a short, cold sting that the BAD describes as usually mild and short-lived, although it varies by body site. Any discomfort afterwards is usually eased with simple pain relief.
Will a skin tag grow back after removal?
The NHS says that once a skin tag is removed it does not usually return. However, people who are prone to skin tags often develop new ones elsewhere over time, particularly in areas of friction. Seborrhoeic keratoses can regrow at the same site after treatment, and new ones may appear, according to the British Association of Dermatologists.
Can I get skin tags removed on the NHS?
Usually not. The NHS considers skin tag removal cosmetic. Evidence-Based Interventions guidance allows removal of benign lesions only when specific criteria are met, such as bleeding more than twice a week for at least four weeks from everyday activity, repeated infections needing antibiotics, or blocked vision. A lesion that looks suspicious for cancer is always assessed and referred.
Is it safe to remove a skin tag at home?
No. The NHS advises not to remove a skin tag yourself unless a GP recommends it, because of the risks of infection, bleeding and scarring. Home methods also skip the assessment that confirms the growth really is a skin tag. Some skin cancers and moles can be mistaken for tags by an untrained eye.
Does blemish removal leave a scar?
Most small benign lesions heal with little or no visible mark, but a small scar or a patch of lighter or darker skin is possible, especially on black and brown skin. Rarely, a raised or keloid scar develops. Tell your clinician about any history of keloids, and ask what the likely mark will look like before treatment.
What is the best way to remove a seborrhoeic keratosis?
The British Association of Dermatologists lists cryotherapy, laser and curettage under local anaesthetic as options. A 2024 randomised trial found seborrhoeic keratoses responded better to cryotherapy than to electrosurgery. Thicker lesions may suit curettage, which also allows histology. Any dark or changing lesion should be checked first, as some can resemble melanoma.
Can cherry angiomas be removed?
Yes. Cherry angiomas, also called Campbell de Morgan spots, are harmless and do not need treatment, but they can be removed with electrocautery or vascular laser for cosmetic reasons. Angiomas that catch or bleed can be removed by curettage and sent for histology. A dark or suddenly black spot should be assessed first, as thrombosed angiomas can look alarming.
How long does it take for the area to heal?
Small snip or cautery wounds usually form a scab that lifts off within one to three weeks. After cryotherapy, swelling settles in two to three days and the scab can take a few weeks to fall off, longer on the legs. Any pink, pale or darker mark then fades gradually over the following months.
Can several skin tags be removed in one appointment?
Often, yes. Many small skin tags can be treated in a single visit once each has been assessed. The number depends on their size, where they are, and how much local anaesthetic is appropriate. Your clinician may suggest treating a test area first if you are concerned about pigment change.
Are skin tags a sign of diabetes?
Not necessarily. Skin tags are very common, found in nearly half of adults in one study. The NHS notes they are more likely with obesity, pregnancy and type 2 diabetes, because severe insulin resistance is thought to encourage them. If you develop many new skin tags, especially with other symptoms such as thirst or tiredness, speak to your GP.
How much does skin tag removal cost in Knightsbridge?
In London, removing a first skin tag or small blemish typically costs about £90 to £350, with additional lesions at the same appointment around £30 to £120 each. An assessment is often £50 to £150, and histology, when needed, about £70 to £150 per sample. These are indicative ranges, and Levirgo confirms your fee in writing.
Can moles be removed the same way as skin tags?
Not usually. Pigmented moles should be assessed with dermoscopy, and if removed they should be excised or shaved so the tissue can be examined in a laboratory. The British Association of Dermatologists advises against laser removal of moles because no sample is left for histology. A mole check is the right first step.
Levirgo Aesthetics Clinic · Knightsbridge
Assessed first, removed with care
Skin tag and benign blemish removal after a thorough skin assessment, with honest advice on marks and healing, on Beauchamp Place in Knightsbridge.
Sources & further reading
- NHS: Skin tags
- British Association of Dermatologists: Seborrhoeic keratosis patient leaflet
- British Association of Dermatologists: Cryotherapy patient leaflet
- British Association of Dermatologists: Melanocytic naevi (pigmented moles) patient leaflet
- Evidence-Based Interventions (Academy of Medical Royal Colleges): Removal of benign skin lesions
- Primary Care Dermatology Society: Cherry angioma (Campbell de Morgan spots)
- Primary Care Dermatology Society: Milia
- Cancer Research UK: Non-melanoma skin cancer symptoms
- Banik R, Lubach D. Skin tags: localization and frequencies according to sex and age. Dermatologica 1987
- Haase O et al. Removal of skin tags: scissor excision versus non-ablative 532nm LBO laser, randomised controlled trial. Arch Dermatol Res 2025
- Sadeghzadeh-Bazargan A et al. Cryotherapy versus electrosurgery for sebaceous hyperplasia, seborrheic keratosis, cherry angioma and skin tag: randomised trial. Health Sci Rep 2024
- Care Quality Commission: Surgical procedures (scope of registration)
This article is general information about benign skin lesions and is not medical advice or a diagnosis. Cosmetic removal does not replace medical assessment: any lesion that is new, changing, bleeding or not healing should be checked by a GP or appropriately trained clinician first. Results and healing vary between individuals. Prices are indicative London market ranges for 2026 and are confirmed in writing after assessment.