

Skin treatments
Keloid Injection in Knightsbridge: Steroid Treatment Explained
Steroid injections are the most common treatment for keloid scars. This guide explains how they work, how many you are likely to need, what the research says about flattening and recurrence, when 5-fluorouracil is added, the side effects to weigh up, and what a course costs in London.
 By Fatemeh, Founder & Lead Practitioner, Levirgo Aesthetics Clinic 18 min read
Reviewed September 2026

What is a keloid, and how is it different from a hypertrophic scar?
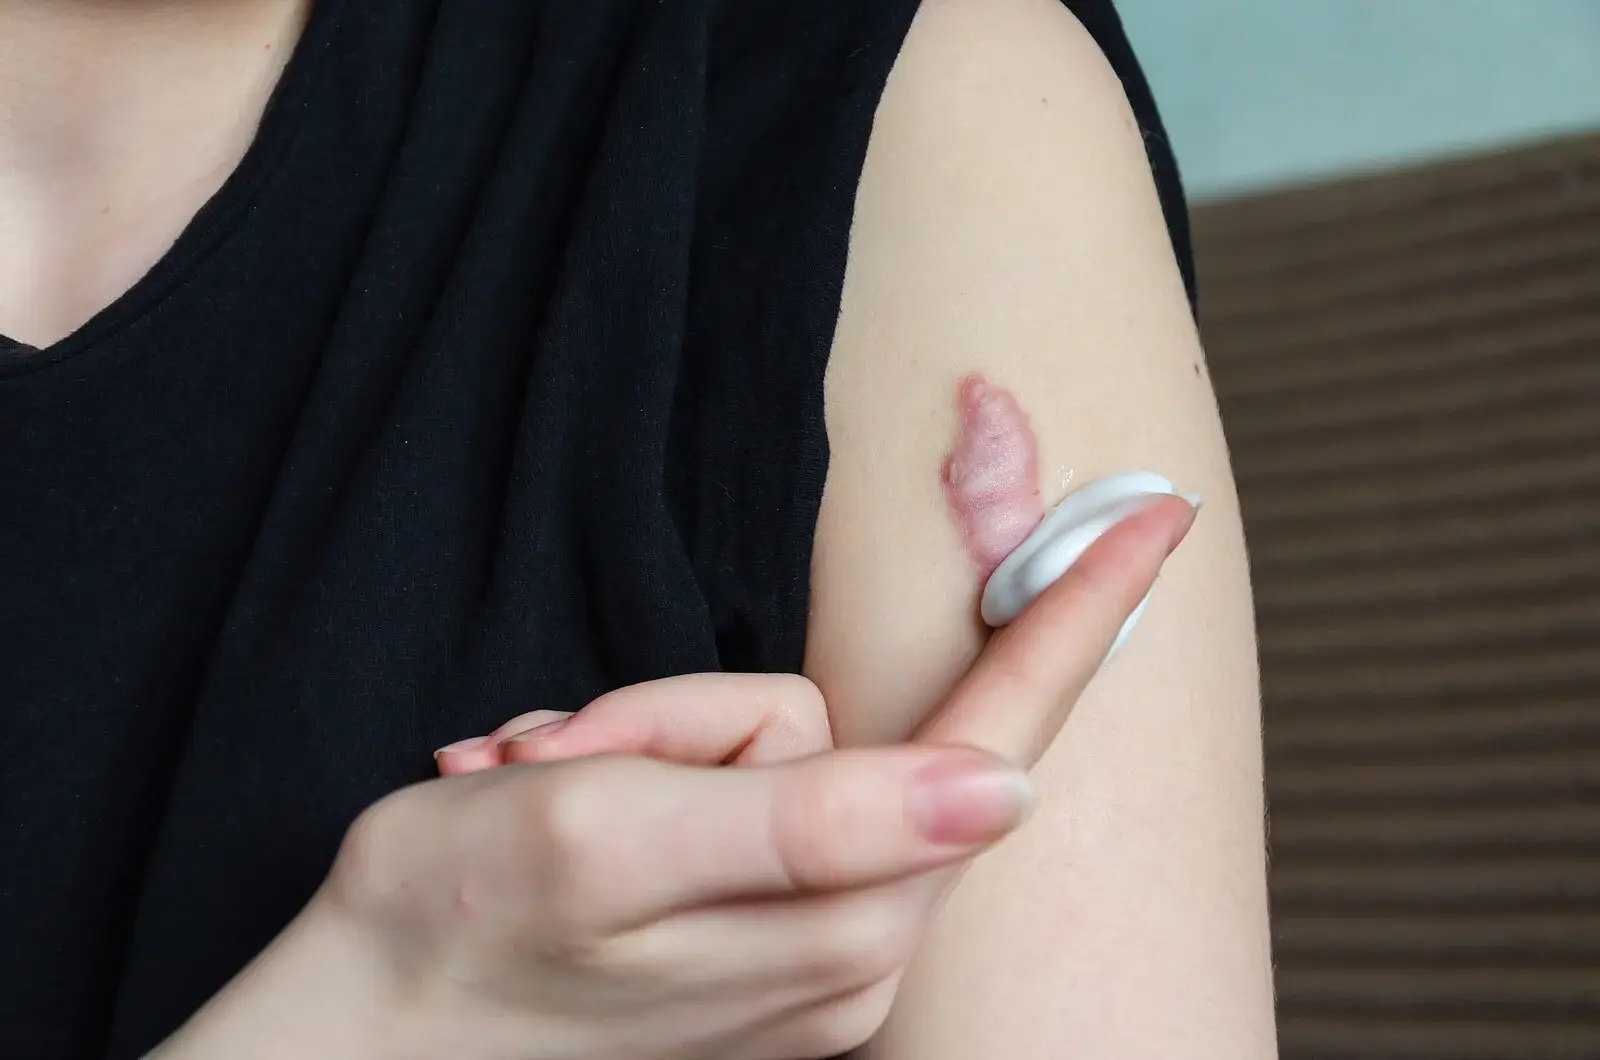
A keloid is a raised, firm scar that grows beyond the edges of the original wound because of excess collagen. A hypertrophic scar is also raised but stays within the wound and usually flattens over time. Keloids can follow tiny injuries such as acne or piercings, and often keep growing for months or years.
Most scars start slightly red and raised, then soften and fade over a year or two. The NHS explains that keloids behave differently: they are usually raised, hard, smooth and shiny, grow for months or years, and become bigger than the original wound. While growing, they may itch or hurt, and near a joint they can restrict movement. The British Association of Dermatologists (BAD) notes that keloids can appear within 3 to 4 weeks of an injury, or take a year or longer.
| Feature | Keloid | Hypertrophic scar |
|---|---|---|
| Size | Spreads beyond the original wound | Stays within the wound edges |
| Trigger | Can follow minor damage such as acne or a piercing, or appear spontaneously | Follows a wound, burn, surgery or acne |
| Course | Grows for months or years; may be permanent | Usually improves and flattens over time |
| Common sites | Chest, shoulders, chin, neck, lower legs, earlobes | Anywhere the skin has been injured |
| Symptoms | May itch or hurt while growing; can restrict a nearby joint | Can be uncomfortable or make movement difficult |
Sources: NHS keloid scars and types of scars pages; British Association of Dermatologists keloids leaflet.
Who is more likely to develop keloids?
- People of south Asian, Chinese, African Caribbean or Black African origin (NHS); the BAD also notes higher rates in people of Hispanic descent.
- People aged roughly 10 to 30; the BAD says keloids most commonly arise between puberty and 30.
- Anyone who has had a keloid before, if the skin is injured again.
- People who are pregnant, when keloids may appear or enlarge.
- People with a family history: the BAD reports that 5% to 10% of Europeans with keloids have an affected relative.
What are keloid injections and how do they work?
Keloid injections place a corticosteroid directly into the scar through a very fine needle. The steroid reduces inflammation and excess collagen production, which softens, flattens and calms the keloid over a series of treatments. Triamcinolone acetonide is the most widely used, and is licensed in the UK for intradermal use in keloids.
Intralesional means “into the lesion”. Rather than applying a steroid to the surface, where little reaches the dense scar tissue, the medicine is injected into the keloid itself. A review of triamcinolone for keloids in Clinical, Cosmetic and Investigational Dermatology describes intralesional corticosteroid injection, alone or combined with other treatments, as the most common approach, and triamcinolone acetonide as the most commonly used steroid.
Triamcinolone acetonide injection is a prescription-only medicine. Its UK Summary of Product Characteristics lists intradermal use for keloids and hypertrophic scars among its indications. That means it must be prescribed by an appropriately qualified prescriber after a proper assessment, and the dose, strength and spacing are tailored to the scar’s size, thickness and site. The review above notes that concentrations of about 10 to 40 mg/mL are usually needed to have an effect on keloids, with lower strengths helping to limit local side effects.
Levirgo’s keloid injection service uses corticosteroid-based injections and, in some cases, combines them with other agents such as 5-fluorouracil or hyaluronidase depending on the scar’s size, location and behaviour. How and why combinations are used is explained below.
How effective are keloid injections?
Steroid injections usually improve keloids, but rarely cure them. A published review reports 50% to 100% regression with corticosteroid injection alone, with recurrence of 33% at 1 year and 50% at 5 years. The BAD similarly warns that up to 50% of keloids grow back, so ongoing follow-up matters.
Response varies widely because keloids vary widely in size, age, thickness and site, and your clinician can only estimate how yours will respond after seeing it. The BAD is candid that there is no cure for keloids and no single treatment has been shown to be better than all others.
Source: Darougheh et al., Clinical and Experimental Dermatology 2009; double-blind randomised trial of 40 patients with keloids or hypertrophic scars given weekly injections for 8 weeks. “Good to excellent” means more than 50% improvement. The patient-reported difference was statistically significant; the observer-rated difference was not.
These numbers explain why a sensible keloid plan talks about control rather than cure: a course to flatten and calm the scar, then monitoring and, if it starts to thicken or itch again, early top-up treatment rather than waiting for it to regrow fully.
Steroid alone or combined with 5-FU: which is better?
Combining triamcinolone with 5-fluorouracil (5-FU) appears more effective than either alone. A 2024 meta-analysis of 13 studies found the combination had 3.45 times the odds of good improvement versus steroid alone, with less telangiectasia. The BAD still describes 5-FU for keloids as experimental and not routinely available.
5-fluorouracil is an anti-cancer medicine that slows the dividing fibroblast cells which lay down scar collagen. Used in small doses inside a keloid, it attacks the problem from a different direction to the steroid. In the meta-analysis by Mavilakandy and colleagues, published in Plastic and Reconstructive Surgery, combination therapy outperformed triamcinolone alone (odds ratio 3.45) and 5-FU alone (odds ratio 4.17), and telangiectasia was less frequent than with steroid alone.
A 2026 network meta-analysis of 24 randomised trials in Aesthetic Surgery Journal reached a similar conclusion: triamcinolone plus 5-FU gave the most consistent improvements in both effectiveness and recurrence control. Botulinum toxin type A, a prescription-only medicine, ranked highest for treatment response but did not significantly reduce recurrence. Verapamil was less effective than triamcinolone, and bleomycin and 5-FU alone gave intermediate results.
| Injected treatment | What the evidence suggests | Points to consider |
|---|---|---|
| Triamcinolone acetonide | Most widely used; 50 to 100% regression in reviews | Licensed for keloids; atrophy and pigment change possible |
| Triamcinolone plus 5-FU | Better efficacy than either alone in meta-analyses | Off-label use of 5-FU; BAD calls it experimental |
| 5-FU alone | Comparable to steroid alone in some trials | Pain more common; not routinely used alone |
| Botulinum toxin type A | Strong response in network meta-analysis; no clear recurrence benefit | Prescription-only; evidence still developing |
| Verapamil | Less effective than triamcinolone | Fewer side effects; higher recurrence |
| Bleomycin | Intermediate results | Specialist use only |
Sources: Mavilakandy et al., Plast Reconstr Surg 2024; Lai et al., Aesthet Surg J 2026; Morelli Coppola et al., Clin Cosmet Investig Dermatol 2018; British Association of Dermatologists keloids leaflet.
Because 5-FU is not licensed for scars, any plan that includes it should be explained clearly, including why it is being suggested for your keloid, the likely extra discomfort, and the alternatives. Most people start with steroid injections alone and add a second agent only if the response is slow.
Who is a good candidate for keloid injections?
Keloid injections suit people with a confirmed keloid or hypertrophic scar that is raised, itchy, painful or bothering them, including after acne, piercings or surgery, and in all skin types. They may be unsuitable if the diagnosis is uncertain, the skin is infected, or medical factors make steroid injections unwise.
- Well suited: firm, raised keloids that itch, ache or catch on clothing; earlobe keloids after piercing; chest and shoulder keloids after acne; hypertrophic scars that have not settled.
- Also useful after excision: injections are often used after a keloid is surgically removed to lower the chance of regrowth. See our guide to keloid removal and excision.
- Needs caution: pregnancy or breastfeeding, poorly controlled diabetes, a history of reactions to steroid injections, or very large keloids where combined treatment may be better.
- Not suitable today: an infected or ulcerated scar, or a lump whose diagnosis is not clear.
When a “keloid” needs a doctor first
The BAD notes that doctors can usually diagnose a keloid by looking, but a skin biopsy may be needed if the diagnosis is uncertain. Seek assessment before any treatment if a lump is growing unusually fast, bleeding, ulcerating, appeared without any injury in an unusual place, or looks different from your other scars. The NHS advises asking for an urgent GP appointment or contacting NHS 111 if a scar is swollen or painful, feels warm, or has pus coming out of it.
Keloids are more common in people with darker skin, who are also more prone to the pigment changes steroid injections can cause. That is not a reason to avoid treatment, but it is a reason to choose a clinician experienced in treating skin of colour, who will start conservatively and review carefully.
What happens during a keloid injection appointment?
After assessing the scar and your medical history, the clinician cleans the skin and uses a very fine needle to inject the steroid solution into the keloid itself. Each keloid takes just a few minutes. You can usually return to normal activities straight away, with a review booked a few weeks later.
- Consultation and assessment
How and when the keloid formed, whether it is growing, itching or painful, previous treatments, other keloids, medical history and medicines. The scar is examined, measured and, with your consent, photographed so progress can be tracked.
- Treatment plan
The clinician explains the proposed medicine, likely number of sessions, spacing, expected results, side effects and alternatives, and you give informed consent.
- Cleansing
The skin over the keloid is cleaned.
- Targeted injection
A fine needle delivers the solution into the body of the scar, not the normal skin around it, which reduces the risk of thinning healthy skin. Keloid tissue is dense, so you may feel pressure and stinging.
- Review
You return after a few weeks. The response and any side effects are assessed before deciding whether to repeat, adjust the dose or change the approach.
Injections into dense keloid tissue can be uncomfortable, particularly on the earlobe and chest. Tell your clinician if you are anxious about pain; numbing options can be discussed.
How many keloid injections will you need, and when will you see results?
Most people need a course of several injections. The BAD describes repeating injections monthly for 4 to 6 months, and Levirgo typically treats every 3 to 4 weeks depending on response. Improvement, including flattening and easing of itch, is gradual over the first few sessions and beyond.
| Stage | What usually happens | What to watch for |
|---|---|---|
| First injection | Keloid may feel slightly softer within weeks; itch may ease | Bruising or tenderness at the site |
| Sessions 2 to 3 | Scar becomes flatter and less firm; symptoms improve further | Early signs of thinning or lightening of nearby skin |
| Sessions 4 to 6 | Continued flattening; decision on whether to stop, space out or add another treatment | Visible vessels (telangiectasia) or pigment change |
| After the course | Maintenance: monitoring and early top-up if the scar thickens again | Returning itch, redness or growth |
Course pattern reflects British Association of Dermatologists guidance (monthly for 4 to 6 months) and Levirgo’s usual 3 to 4-weekly schedule. Individual responses vary, and many keloids flatten only partly.
Spacing matters. Injecting too often increases the risk of skin atrophy; too infrequently and the scar can rebound between sessions. Your clinician should adjust dose and interval to how your keloid responds rather than following a fixed number of sessions. If there has been little change after several well-placed injections, it is time to discuss combination treatment or other options.
Help your treatment work
Keep follow-up appointments, photograph the scar in the same light each month, avoid friction and tight straps over the area, and use silicone gel or sheeting between sessions if your clinician recommends it. The NHS also advises protecting scars from the sun for at least a year and using SPF 30 or higher.
Itchy, raised or growing scar?
Have it assessed and get a tailored injection plan, with honest advice on results, side effects and recurrence.
What are the side effects of keloid injections?
Common effects are pain, bruising and tenderness at the injection site. The main longer-term risks are skin and fat atrophy (a dip or thinning), lighter or darker skin, and telangiectasia (visible small vessels). Rarely, repeated or large doses can have systemic steroid effects. Most local effects improve over time.
The BAD warns that steroid injections can make the skin thin, fragile and pale. The Morelli Coppola review lists local side effects including telangiectasias, skin and subcutaneous fat atrophy, hypopigmentation and hyperpigmentation, and, uncommonly, skin necrosis and ulceration, with a greater risk when steroid is accidentally injected into the surrounding normal tissue. Systemic effects such as Cushing’s syndrome are rare and have mostly been reported in children. The medicine’s product information also notes that corticosteroids can raise blood glucose, which matters for people with diabetes.
| Side effect | What it looks like | How the risk is reduced |
|---|---|---|
| Pain and bruising | Stinging during injection; small bruise | Fine needle, slow injection, numbing options |
| Atrophy | A dip or thinning in or around the scar | Accurate placement into the keloid; lowest effective strength |
| Hypopigmentation | Paler patch, more noticeable on darker skin | Conservative dosing; careful review between sessions |
| Telangiectasia | Fine red visible vessels | Dose adjustment; combination with 5-FU associated with less telangiectasia |
| Systemic steroid effects | Rare; raised blood sugar possible in diabetes | Keeping doses within product limits; monitoring glucose if diabetic |
Sources: British Association of Dermatologists keloids leaflet; Morelli Coppola et al., 2018; Mavilakandy et al., 2024; triamcinolone acetonide UK Summary of Product Characteristics.
Contact the clinic or your GP if the injection site becomes hot, increasingly painful, swollen or discharges pus, which could suggest infection. If you notice a dip or pale patch developing, mention it at your next review rather than waiting; adjusting the plan early usually prevents it worsening.
How do injections compare with other keloid treatments?
Injections are usually first-line. The NHS also lists silicone gels or dressings, cryotherapy and laser, and says surgery alone is not usually recommended because keloids tend to grow back bigger. Excision is generally combined with injections, compression or radiotherapy to lower recurrence.
| Treatment | Role | Evidence and trade-offs |
|---|---|---|
| Steroid injections | First-line for most keloids | 50 to 100% regression; recurrence common; atrophy and pigment risk |
| Silicone gel or sheeting | Adjunct and prevention | Cochrane review: weak, poor-quality evidence of benefit |
| Compression | Earlobes and torso, often after excision | Useful in selected sites (BAD) |
| Cryotherapy | Alone or with injections | Can cause loss of pigment (BAD) |
| Laser | Redness and texture, often with injections | Helps especially combined with steroid; high recurrence alone |
| Surgical excision | Large or stalked keloids, earlobes | High regrowth if used alone; needs adjuvant treatment |
| Radiotherapy after excision | Specialist option for resistant keloids | Small risk of radiation-induced cancer, so rarely used (BAD) |
Sources: NHS keloid scars; British Association of Dermatologists keloids leaflet; O’Brien and Jones, Cochrane Database of Systematic Reviews 2013; Morelli Coppola et al., 2018.
For many people the best plan is a combination: injections to flatten and calm the keloid, silicone and sun protection to support it, and, for large or pedunculated keloids, excision followed by preventive injections. Our separate article on keloid removal and recurrence prevention covers surgery in depth, and the scar treatment page covers other scar types.
How much do keloid injections cost in London?
In London, a keloid injection session typically costs about £120 to £250 for a small keloid and £200 to £350 for larger or multiple keloids. A typical course of 4 to 6 sessions is roughly £600 to £1,600, plus a consultation of about £50 to £150. These are indicative ranges.
| Item | Typical London range | Notes |
|---|---|---|
| Consultation and assessment | £50 to £150 | Often redeemable against treatment |
| Injection session, small keloid | £120 to £250 | Per session |
| Injection session, larger or multiple keloids | £200 to £350 | Per session |
| Typical course of 4 to 6 sessions | £600 to £1,600 | Depends on size, number and response |
Indicative London market ranges, not Levirgo’s price list. Your fee is confirmed in writing after assessment. Keloid treatment may be available on the NHS through your GP or dermatology service in some circumstances.
Ask whether review appointments are included, whether combination agents cost extra, and how many sessions the clinician realistically expects for your scar. Because keloids can recur, it is also worth asking what a top-up session would cost later.
How do you choose a clinic for keloid injections?
Choose a clinic where a qualified prescriber examines you in person before prescribing, the diagnosis is confirmed, side effects and recurrence are explained honestly, progress is photographed, and there is experience of treating keloids in darker skin tones. Avoid anyone promising permanent removal.
Corticosteroid injections are prescription-only medicines. The General Medical Council requires doctors to physically examine patients before prescribing injectable cosmetic medicines and not to prescribe them remotely; the same principle of face-to-face assessment is good practice for medical injections such as keloid treatment. You can check a doctor on the GMC register, a nurse prescriber on the NMC register, and a clinic’s registration with the Care Quality Commission.
- Is the person prescribing the medicine the one who assessed your scar?
- Have they explained the likely number of sessions and what “improvement” realistically means?
- Have they discussed atrophy and pigment change, especially for your skin tone?
- Will your scar be measured and photographed at each visit?
- Is there a plan if the keloid does not respond, or comes back?
- Are claims realistic? Nobody can honestly guarantee a keloid will not return.
Why choose Levirgo for keloid injections in Knightsbridge?
Levirgo Aesthetics Clinic at 6 Beauchamp Place, Knightsbridge, SW3 1NG, near Harrods and Knightsbridge Underground station, offers corticosteroid-based keloid injections tailored to each scar’s size, location and behaviour, for all skin types, in a discreet setting, with excision and combined plans available when injections alone are not enough.
Every treatment starts with a careful consultation to confirm the diagnosis and plan the most suitable approach. Injection plans are adjusted according to how your scar responds, and we are open about what injections can and cannot achieve. For larger keloids, excision and injection options are available under one roof, so your plan can change as your scar does.
Beauchamp Place is a few minutes’ walk from Knightsbridge station on the Piccadilly line, with easy access from South Kensington, Chelsea, Mayfair and Kensington. Book online or get in touch to discuss your scar. You can also explore our wider skin treatments.
Frequently asked questions
Do keloid injections work?
For most people they help. Reviews report 50% to 100% regression with corticosteroid injections. However, keloids frequently return: one review reports recurrence of about 33% at 1 year and 50% at 5 years, and the British Association of Dermatologists says up to half grow back. Injections are best seen as control rather than a permanent cure.
How many keloid injections will I need?
Most keloids need a course rather than a single injection. The British Association of Dermatologists describes injections repeated monthly for 4 to 6 months, and Levirgo typically treats every 3 to 4 weeks depending on response. Small, recent keloids may need fewer sessions; large or old keloids often need more, or a combined approach.
Do keloid injections hurt?
They can sting, because keloid tissue is dense and the solution has to be pushed into it. A very fine needle is used and each keloid takes just a few minutes. Discomfort is usually brief. Earlobes and the chest can be more sensitive, and your clinician can discuss ways to make the injection more comfortable.
What is injected into a keloid?
Usually a corticosteroid, most commonly triamcinolone acetonide, a prescription-only medicine licensed in the UK for intradermal use in keloids and hypertrophic scars. In some cases it is combined with other agents such as 5-fluorouracil or hyaluronidase, depending on the scar’s size, location and behaviour. Any combination should be explained fully before treatment.
Can keloid injections make the scar worse?
They do not usually make the keloid itself grow, but steroid injections can cause side effects around it, including a dip from skin or fat thinning, a paler or darker patch, and visible small blood vessels. These are more likely with higher doses or if steroid reaches the normal surrounding skin. Most improve over months, which is why careful dosing and review matter.
When will I see results from keloid injections?
Some people notice the scar feels softer or less itchy after the first injection or two. Visible flattening is gradual and usually builds over the first few sessions and beyond. Photographs taken at each visit make progress easier to judge than memory, because change from session to session can be subtle.
Are keloid injections safe for dark skin?
Yes, keloid injections are used in all skin types, and keloids are more common in people of African, Caribbean, south Asian and Chinese origin. Darker skin is more likely to show pigment change, particularly lightening, after steroid injections, so a conservative approach and experienced clinician are important. Discuss this risk before starting treatment.
Will my keloid come back after injections?
It might. Recurrence is common with every keloid treatment. One review reports recurrence of around a third at 1 year and half at 5 years after steroid injections. Avoiding new injury to the area, using silicone if advised, and returning early for a top-up injection if the scar starts to thicken or itch can help keep it under control.
Is 5-FU better than steroid injections for keloids?
On its own, 5-FU performs similarly to steroid in some trials but tends to be more painful. Combined with triamcinolone, it has shown better results than either alone in meta-analyses, with less telangiectasia than steroid alone. The British Association of Dermatologists describes 5-FU for keloids as experimental and not routinely available, so it should be discussed carefully.
Can I have keloid injections while pregnant?
Tell your clinician if you are pregnant, trying to conceive or breastfeeding. Keloids may appear or grow during pregnancy. The product information for triamcinolone advises that corticosteroids should only be prescribed in pregnancy when the benefits outweigh the risks, so decisions need individual medical advice. Silicone and protecting the scar from friction are gentle options in the meantime.
Can keloids be removed without surgery?
Keloids cannot usually be removed completely without surgery, but many can be made much flatter, softer and less itchy with injections, silicone, compression, cryotherapy or laser. The NHS notes that surgery on its own is not usually recommended because keloids are likely to grow back bigger, so non-surgical treatment is often the first step.
How much do keloid injections cost in Knightsbridge?
In London, a keloid injection session typically costs about £120 to £250 for a small keloid or £200 to £350 for larger or multiple keloids. A course of 4 to 6 sessions is roughly £600 to £1,600, plus a consultation of about £50 to £150. These are indicative ranges; Levirgo confirms your fee in writing after assessment.
Levirgo Aesthetics Clinic · Knightsbridge
Calmer, flatter keloid scars, with realistic expectations
Corticosteroid-based keloid injections tailored to your scar and skin tone, with excision and combined plans available, on Beauchamp Place in Knightsbridge.
Sources & further reading
- NHS: Keloid scars
- NHS: Scars (types of scars and when to get help)
- British Association of Dermatologists: Keloids patient leaflet
- Electronic Medicines Compendium: triamcinolone acetonide 10mg/ml intra-articular/intradermal injection, Summary of Product Characteristics
- Morelli Coppola M et al. Triamcinolone acetonide intralesional injection for the treatment of keloid scars. Clin Cosmet Investig Dermatol 2018
- Mavilakandy A et al. Combination triamcinolone and 5-fluorouracil versus monotherapy for keloids and hypertrophic scars: systematic review and meta-analysis. Plast Reconstr Surg 2024
- Lai IC et al. Comparative efficacy and recurrence risk of intralesional therapies for hypertrophic scars and keloids: network meta-analysis. Aesthet Surg J 2026
- Darougheh A et al. Intralesional triamcinolone alone or with 5-fluorouracil for keloid and hypertrophic scars. Clin Exp Dermatol 2009
- O’Brien L, Jones DJ. Silicone gel sheeting for preventing and treating hypertrophic and keloid scars. Cochrane Database Syst Rev 2013
- General Medical Council: Deciding if it is safe to prescribe (including remote prescribing of injectable cosmetic medicines)
This article is general information about keloid scars and their treatment and is not medical advice. Keloid injections use prescription-only medicines and require an in-person assessment by a qualified prescriber. Results vary, keloids can recur, and no outcome can be guaranteed. If a scar is hot, swollen, discharging pus or rapidly changing, seek medical advice promptly. Prices are indicative London market ranges for 2026 and are confirmed in writing after assessment.