

Skin treatments
Keloid Removal and Excision in Knightsbridge: Stopping Recurrence
Cutting out a keloid is the easy part. Keeping it from growing back is the real challenge. This guide explains why surgery alone fails so often, what the evidence says about combining excision with steroid injections, compression and radiotherapy, which surgical techniques help, and what recovery really involves.
 By Fatemeh, Founder & Lead Practitioner, Levirgo Aesthetics Clinic 17 min read
Reviewed September 2026

When is keloid removal or excision the right option?
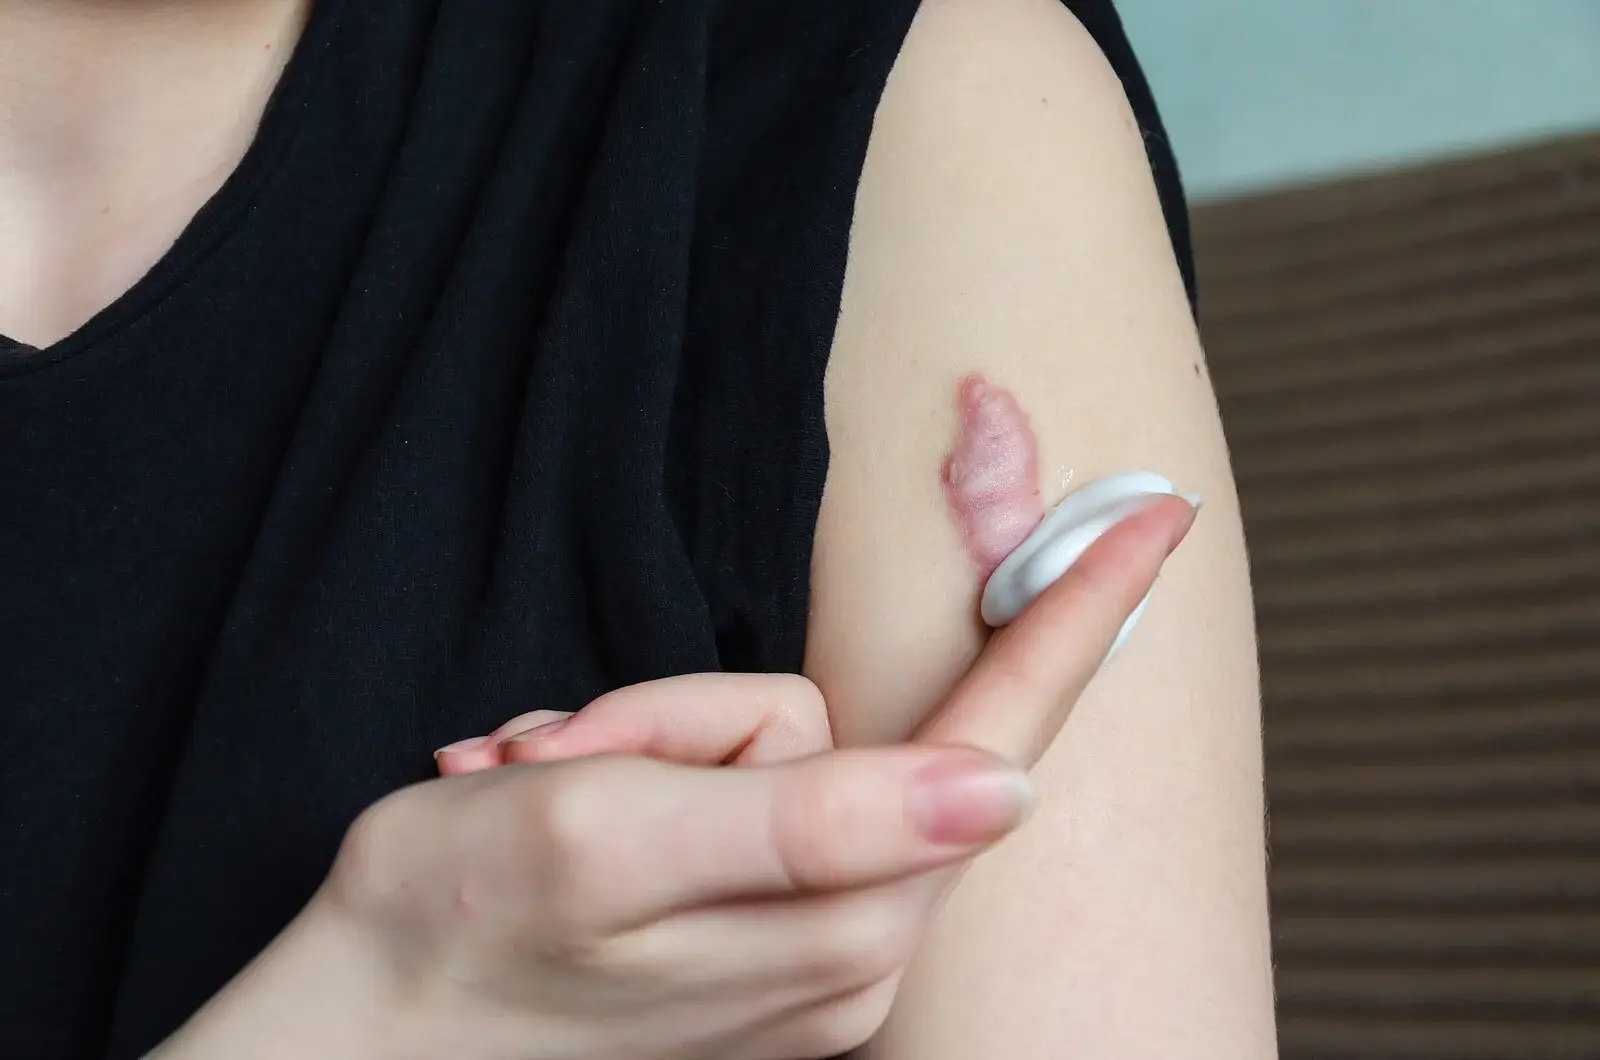
Excision is considered for keloids that are large, bulky, stalked or on the earlobe, or that have not responded to injections, and almost always as part of a combined plan. The NHS and British Association of Dermatologists caution that surgery on its own is rarely successful because keloids tend to regrow.
Most keloids are treated first without surgery, usually with steroid injections, silicone and sometimes cryotherapy or laser. Our guide to keloid injections covers that route. Surgery becomes a sensible conversation when a keloid is too thick for injections alone to make a meaningful difference, when it hangs from a stalk or forms a ball on the earlobe, or when it restricts movement or repeatedly catches and bleeds.
A 2022 update of international scar-treatment algorithms by Rei Ogawa in Plastic and Reconstructive Surgery suggests that small, single keloids can be treated radically by surgery with adjuvant therapy, or alternatively with non-surgical multimodal treatment, while large and multiple keloids may suit partial or core excision that reduces the thick, hard areas or the number of keloids.
| Keloid type | Usual first approach | Where excision fits |
|---|---|---|
| Small, flat or early keloid | Steroid injections, silicone | Rarely needed |
| Earlobe keloid after piercing | Injections for small ones; excision for bulky ones | Wedge or core excision with adjuvant treatment |
| Stalked (pedunculated) keloid | Excision is often practical | Excision plus injections or compression |
| Large chest or shoulder keloid | Multimodal non-surgical treatment | Partial excision or specialist surgery with adjuvant therapy |
| Many acne keloids | Non-surgical treatment | Selected lesions only |
| Keloid that returned after surgery | Injections, then reassess | Only with a stronger adjuvant plan |
Based on NHS and British Association of Dermatologists guidance and Ogawa, Plast Reconstr Surg 2022. Every keloid is different and the plan is individual.
Why does a keloid come back after surgery alone?
Because cutting out a keloid creates a fresh wound in skin that is already prone to overhealing. The same process that made the original keloid can start again in the new scar, often worsened by tension on the wound. Reviews report recurrence of 45% to 100% after surgery alone.
Keloids are driven by excessive collagen production and persistent inflammation in the healing skin. Removing the visible lump does not remove that tendency. The BAD puts it plainly: surgically removing a keloid is rarely a success on its own, because it can cause a larger wound in which the keloid is likely to regrow. The NHS adds that the new keloid may grow back bigger than the one removed.
Tension is a major factor. Ogawa notes that keloids rarely form on the scalp and front of the lower leg, where stretching tension is low, and are common on the chest, shoulders and upper back, where skin is constantly pulled by movement and breathing. After surgery on these sites, he recommends techniques that limit tension in the deeper skin, such as flaps, Z-plasties and subcutaneous and deep fascial tension-reducing sutures.
- A new wound restarts the abnormal healing response in keloid-prone skin.
- Tension across the closure, especially on the chest, shoulders and upper back, stimulates scar growth.
- Inflammation or infection in the healing wound increases the risk of pathological scarring.
- No adjuvant treatment leaves nothing to suppress early regrowth in the first weeks and months.
- Late follow-up means early signs, such as itch and firmness, are missed until the keloid has re-formed.
How much do combined treatments reduce keloid recurrence?
Substantially. A 2026 systematic review of 21 studies and more than 8,627 patients found recurrence of 6.6% to 33% with adjuvant steroid injections, 3.1% to 15% with brachytherapy and 10.7% and 14% with compression, and concluded that combining surgery with adjuvant therapy is the most effective strategy.
The review by Wojarska and colleagues could not pool results into a single meta-analysis because protocols varied so much, but the direction was consistent: multimodal approaches significantly reduce recurrence compared with surgery alone, and combination drug treatments did better than single agents. Adjuvant 5-fluorouracil also reduced recurrence compared with surgery alone.
Lower is better. Sources: Mankowski et al., Ann Plast Surg 2017 (meta-analysis of 72 studies, 9,048 keloids; RT means radiotherapy, brachy means brachytherapy) and Shin et al., Plast Reconstr Surg 2016 (meta-analysis of 25 studies of ear keloids). Surgery alone, not shown, recurs in 45% to 100% of cases. Figures come from different study populations and are not a head-to-head comparison.
What about radiotherapy after excision?
Radiotherapy delivered shortly after excision is one of the most studied adjuvant treatments. In Mankowski’s meta-analysis, radiotherapy after surgery was followed by less recurrence than radiotherapy alone (22% versus 37%), brachytherapy performed best, and chest keloids had the highest recurrence. The most common side effect was change in skin pigmentation. The BAD notes that radiotherapy carries a small risk of causing skin cancer and is therefore rarely used. It is delivered by hospital radiotherapy teams, so for most people in the UK it is a specialist referral for resistant keloids rather than a routine option.
What does a combined keloid removal plan involve?
A combined plan pairs careful, tension-reducing excision with one or more adjuvant treatments, most often steroid injections into the wound and new scar over the following months, pressure dressings or pressure earrings, silicone, and close follow-up so early regrowth is treated immediately.
| Component | What it involves | Evidence and notes |
|---|---|---|
| Tension-reducing excision | Removal with deep sutures, Z-plasty or flap where needed | Recommended by Ogawa 2022 to limit dermal tension |
| Steroid injections | Injections into the wound edges and new scar over several months | 6.6 to 33% recurrence; 5-year rates 8 to 50% in reviews |
| 5-fluorouracil | Sometimes combined with steroid | Reduced recurrence versus surgery alone; off-label use |
| Compression | Pressure earrings or dressings worn for months | 10.7% and 14% recurrence; best evidence on ears |
| Silicone gel or sheeting | Applied once the wound has healed | Cochrane: weak, poor-quality evidence |
| Radiotherapy | Specialist hospital treatment soon after surgery | 14 to 29.3% (external beam), 3.1 to 15% (brachytherapy); small cancer risk |
Sources: Wojarska et al., Medicina 2026; Morelli Coppola et al., Clin Cosmet Investig Dermatol 2018; Ogawa, Plast Reconstr Surg 2022; O’Brien and Jones, Cochrane 2013; British Association of Dermatologists keloids leaflet.
Surgical techniques that matter
How a keloid is removed can influence whether it returns. Ogawa’s algorithm recommends wedge excision for earlobe keloids and core excision for keloids on the ear cartilage, and describes low recurrence in case series when these were combined with radiotherapy or steroid injections. For the chest, shoulders and upper arm, it describes tension-reduction suturing and Z-plasty, sometimes with flaps, to spread and reduce tension on the closure. Clinical experience in that review suggests the suturing method matters more than the suture material.
At Levirgo, keloid excision is performed under local anaesthesia, and aftercare to prevent regrowth may include pressure dressings or preventative steroid therapy. Where a keloid would benefit from radiotherapy or complex reconstruction, the right step is referral to a specialist hospital team.
Who is a good candidate for keloid excision?
Good candidates have a clearly diagnosed keloid that is bulky, stalked or on the earlobe, understand that recurrence is possible, and are willing to commit to months of follow-up and adjuvant treatment. Excision is less suitable for large chest keloids, multiple acne keloids, or anyone unable to attend aftercare.
- Often suitable: earlobe keloids after piercing; stalked keloids; a single bulky keloid that injections have not flattened; keloids that restrict movement or repeatedly bleed.
- Needs careful discussion: keloids on the chest, shoulders or upper back, where tension and recurrence are highest; previous recurrence after surgery; very large keloids.
- Usually better treated without surgery first: small, flat or recent keloids; many acne keloids.
- Not suitable today: active infection, uncontrolled medical conditions affecting healing, or an unclear diagnosis.
Make sure it is really a keloid
The BAD says a skin biopsy can be taken if the diagnosis of a keloid is uncertain. Ask for a medical assessment before any removal if a lump appeared without an obvious injury, is growing unusually fast, bleeds or ulcerates, or feels different from a scar. The NHS advises asking for an urgent GP appointment or calling NHS 111 if a scar is swollen or painful, feels warm, or has pus coming from it.
If you are prone to keloids
The BAD advises people at increased risk of keloids to avoid unnecessary skin trauma, such as tattoos, body piercing and non-essential surgery, particularly on the chest and earlobes. If you need surgery for another reason, tell your surgeon about your keloid history so preventive steps can be planned from the start.
What happens during keloid excision?
After a detailed consultation and consent, the area is numbed with local anaesthesia, the keloid is carefully excised and the wound closed to minimise tension. The procedure typically takes 30 to 60 minutes depending on size. Adjuvant treatment, such as steroid injection or a pressure dressing, may begin on the day.
- In-depth consultation
The keloid’s type, size, location and history are assessed along with your medical history, and excision, injections or a combination are recommended. Recurrence risk is discussed honestly before you decide.
- Planning and consent
The incision, closure method and adjuvant plan are explained, including how many follow-up appointments to expect. Photographs are taken with your consent.
- Local anaesthesia
The area is numbed. The injection stings for a few seconds, then the area goes numb.
- Precise removal
The keloid is excised and the wound is closed in a way that reduces tension. Tissue can be sent for laboratory analysis if there is any doubt about the diagnosis.
- Adjuvant treatment and dressing
Depending on your plan, preventative steroid therapy may be given and a pressure dressing applied. You go home the same day with written aftercare.

Considering keloid removal?
Get an honest assessment of whether excision, injections or a combination is most likely to keep your keloid from returning.
What is recovery like after keloid removal?
Most people go home the same day and rest for the remainder of it. Non-dissolvable stitches usually stay in for 7 to 14 days, and exercise can often resume 1 to 2 weeks after stitches are removed. The scar looks pink and may be slightly raised for months, and follow-up to prevent regrowth continues well beyond that.
| Timeframe | What to expect | What to do |
|---|---|---|
| Day of surgery | Numbness wears off; mild discomfort | Rest; paracetamol if needed; keep dressing on |
| First 48 hours | Some tenderness and possible bruising | Keep the dressing clean and dry; avoid baths |
| Days 7 to 14 | Stitches removed; any scab usually comes off by about 14 days | Attend stitch removal and first review |
| Weeks 2 to 4 | New scar pink and may feel slightly raised | Resume exercise gently 1 to 2 weeks after stitches out |
| Months 1 to 6 | Adjuvant injections or compression as planned | Report any itch, firmness or thickening early |
| Months 6 to 12 and beyond | Scar gradually fades; recurrence risk continues | Keep follow-up appointments and protect the scar from the sun |
General excision timings from University Hospitals Dorset NHS Foundation Trust skin excision leaflet; sun protection advice from NHS scars guidance. Your own timeline depends on keloid size, site and adjuvant plan.
The most important part of recovery is noticing early signs of regrowth. Ogawa’s algorithm advises that if the new scar starts to harden, steroid treatment should begin straight away, escalating to injections if the firmness persists. In practice that means itch, a ridge of firmness or a scar that is widening rather than fading should prompt a call to the clinic rather than a wait for your next appointment.
- Avoid stretching the area, heavy lifting and gym work until your clinician says it is safe, especially on the chest and shoulders.
- Wear pressure earrings or dressings exactly as instructed; compression works only if it is worn consistently.
- Once the wound has healed, use silicone gel or sheeting if advised.
- Keep the scar covered in the sun for at least a year and use SPF 30 or higher, as the NHS recommends for scars.
- Seek advice for increasing pain, redness, swelling, a fever or discharge from the wound.
What are the risks of keloid removal?
The biggest risk is recurrence, sometimes with a larger keloid. Other risks of skin excision include bleeding, bruising, infection, numbness and wound opening. Adjuvant steroid injections can cause skin thinning and pigment change, and radiotherapy carries pigment change and a small long-term cancer risk.
| Risk | How it presents | How it is reduced |
|---|---|---|
| Recurrence | Itch, firmness and thickening in the new scar, often within months | Adjuvant treatment, tension-reducing closure, early review |
| Larger keloid | Regrowth bigger than the original | Avoid surgery alone; choose candidates carefully |
| Infection | Increasing redness, pain, heat, pus or fever | Sterile technique; wound care; prompt review |
| Wound opening | Edges separate, often with strain or infection | Tension-reducing sutures; limiting movement early |
| Numbness or nerve pain | Reduced feeling around the scar, usually temporary | Careful technique; discussed in consent |
| Steroid side effects | Thinning, pale or dark patches, visible vessels | Accurate injection into scar; conservative dosing |
| Radiotherapy effects | Pigment change; small long-term cancer risk | Specialist selection; rarely used |
Sources: NHS keloid scars; British Association of Dermatologists keloids leaflet; University Hospitals Dorset skin excision leaflet (general risks of skin excision); Mankowski et al., 2017; Morelli Coppola et al., 2018.
Excision leaves a scar of its own, usually longer than the keloid. For small keloids that are not causing symptoms, the honest advice is sometimes that injections, silicone and patience give a better long-term outcome than surgery. For a clearer picture of non-surgical options, see our scar treatment page.
How much does keloid removal cost in London?
In London, excision of an earlobe or small keloid typically costs about £600 to £1,400, and larger keloids £1,200 to £2,500 or more. Adjuvant injection sessions are roughly £120 to £350 each, plus a consultation of £50 to £150. Radiotherapy, if needed, is arranged and priced separately by a specialist.
| Item | Typical London range | Notes |
|---|---|---|
| Consultation and planning | £50 to £150 | Often redeemable against treatment |
| Earlobe or small keloid excision | £600 to £1,400 | Local anaesthetic; closure and dressing |
| Larger keloid excision | £1,200 to £2,500 or more | Depends on size, site and closure technique |
| Adjuvant injection sessions | £120 to £350 each | Usually several over the following months |
Indicative London market ranges, not Levirgo’s price list. Your fee is confirmed in writing after assessment. Radiotherapy and complex reconstruction are specialist services priced separately.
When comparing quotes, count the whole plan rather than the operation alone: the adjuvant injections or compression, review appointments, and what happens and costs if the keloid starts to return. A cheaper excision without follow-up is the approach most likely to end in recurrence.
How do you choose a clinic for keloid removal in London?
Choose a CQC-registered clinic where a doctor experienced in skin surgery assesses the keloid, explains recurrence honestly, uses tension-reducing technique, builds in adjuvant treatment and follow-up from the start, and can refer you for radiotherapy or complex surgery when your keloid needs it.
In England, surgical procedures carried out by healthcare professionals, including excision of lesions, are regulated by the Care Quality Commission. You can check a provider on the CQC website and a doctor on the GMC register. Beyond regulation, look for a clear plan for what happens after the stitches come out.
- Has the clinician explained why excision is better than injections for your keloid?
- Have you been told the realistic chance of recurrence for your keloid’s site?
- Is adjuvant treatment, such as steroid injections or compression, included in the plan?
- How often will you be reviewed, and for how long?
- What happens if the keloid starts to come back?
- Would they refer you to a specialist team for radiotherapy or reconstruction if needed?
Why choose Levirgo for keloid removal in Knightsbridge?
Levirgo Aesthetics Clinic at 6 Beauchamp Place, Knightsbridge, SW3 1NG, near Harrods and Knightsbridge Underground station, offers keloid excision under local anaesthesia and steroid injection options under one roof, with plans that combine both where needed and aftercare designed to minimise recurrence.
We treat keloid removal as a months-long plan rather than a single procedure. Your consultation looks at the keloid’s type, location and history, and we recommend excision, injections or a combination depending on what is most likely to give a lasting result. If a non-surgical route is wiser for your keloid, we will say so.
The clinic is on Beauchamp Place, a few minutes’ walk from Knightsbridge station on the Piccadilly line, and convenient for patients from Belgravia, Sloane Square, Chelsea and South Kensington. Book online or contact us to arrange an assessment, or browse our skin treatments.
Frequently asked questions
Will my keloid come back after it is removed?
It might. After surgery alone, reviews report recurrence in 45% to 100% of cases, and the NHS warns the keloid may grow back bigger. Combining excision with adjuvant treatment lowers the risk considerably: a 2026 systematic review found recurrence of 6.6% to 33% with steroid injections and 3.1% to 15% with brachytherapy. No approach can guarantee a keloid will not return.
Is keloid removal surgery painful?
Keloid excision is performed under local anaesthesia, which stings for a few seconds before the area goes numb, so the procedure itself should not be painful. Some discomfort is common once the anaesthetic wears off, usually manageable with paracetamol. Follow-up steroid injections into the scar can sting briefly.
How long does keloid excision take?
At Levirgo, keloid excision under local anaesthesia typically takes 30 to 60 minutes, depending on the size of the keloid. Smaller earlobe keloids are usually quicker. You go home the same day, and follow-up appointments for stitch removal and adjuvant treatment are planned in advance.
How long is recovery after keloid removal?
Most people return to normal daily activities quickly. Non-dissolvable stitches usually stay in for 7 to 14 days, and exercise can often resume 1 to 2 weeks after they are removed. The new scar is pink and may feel slightly raised for months, and follow-up to prevent recurrence typically continues for many months after surgery.
Why is surgery alone not recommended for keloids?
Because removing a keloid creates a new wound in skin that tends to overheal, the same abnormal scarring can start again. The British Association of Dermatologists says excision alone is rarely a success, and the NHS says surgery is not usually recommended on its own. Adding steroid injections, compression or, in specialist settings, radiotherapy reduces recurrence.
What is the best treatment after keloid excision?
There is no single best option for everyone. Steroid injections are widely used and practical; compression works well for earlobe keloids; radiotherapy is effective but rarely used because of a small long-term cancer risk. A meta-analysis of ear keloids found similar recurrence after excision with steroid (15.4%) or radiotherapy (14.0%). The choice depends on site, size and history.
Can an earlobe keloid be removed?
Yes. The ear is a common site for keloids, often after piercing, and bulky earlobe keloids are frequently treated with excision. Techniques such as wedge or core excision are combined with adjuvant treatment, such as steroid injections or pressure earrings worn for months, to reduce recurrence. Avoid re-piercing the same ear if you are prone to keloids.
Does keloid removal leave a scar?
Yes. Excision replaces the keloid with a surgical scar, which is usually longer than the keloid but, if healing goes well, flatter and less noticeable. The aim is a fine, flat scar. Protecting it from the sun, following pressure and silicone advice, and treating any early thickening promptly all improve the final result.
Can keloids on the chest be removed?
They can, but chest keloids have some of the highest recurrence rates because the skin is under constant tension. Non-surgical treatment is usually tried first. If excision is considered, it should involve tension-reducing techniques and strong adjuvant treatment, and some chest keloids are best managed by specialist hospital teams, including radiotherapy where appropriate.
Is radiotherapy safe after keloid removal?
Postoperative radiotherapy reduces recurrence and is used in specialist centres, but the British Association of Dermatologists notes it carries a small risk of causing skin cancer, so it is rarely used. The most commonly reported side effect is skin pigmentation change. It is delivered by hospital radiotherapy teams after careful selection, not in aesthetic clinics.
Can I have keloid removal on the NHS?
The NHS advises seeing a GP if you think you have a keloid scar and it is bothering you; the GP can recommend treatments such as steroid injections or silicone, and getting treatment early may help stop it growing. What is available varies locally. The NHS says surgery on its own is not usually recommended because the keloid is likely to grow back bigger.
How much does keloid removal cost in Knightsbridge?
In London, excision of an earlobe or small keloid typically costs about £600 to £1,400, and larger keloids £1,200 to £2,500 or more. Adjuvant injection sessions are around £120 to £350 each, plus a consultation of £50 to £150. These are indicative ranges; Levirgo confirms your plan and fee in writing after assessment.
Levirgo Aesthetics Clinic · Knightsbridge
Keloid removal planned to prevent regrowth
Excision under local anaesthesia, steroid injections and aftercare combined into one plan, on Beauchamp Place in Knightsbridge.
Sources & further reading
- NHS: Keloid scars
- NHS: Scars
- British Association of Dermatologists: Keloids patient leaflet
- Ogawa R. The most current algorithms for the treatment and prevention of hypertrophic scars and keloids: a 2020 update. Plast Reconstr Surg 2022
- Wojarska M et al. Surgical excision with adjuvant therapies in the management of keloids: a systematic review. Medicina 2026
- Mankowski P et al. Optimizing radiotherapy for keloids: a meta-analysis comparing recurrence rates between radiation modalities. Ann Plast Surg 2017
- Shin JY et al. Triamcinolone versus radiation therapy for ear keloids after surgical excision: systematic review and meta-analysis. Plast Reconstr Surg 2016
- Morelli Coppola M et al. Triamcinolone acetonide intralesional injection for the treatment of keloid scars. Clin Cosmet Investig Dermatol 2018
- O’Brien L, Jones DJ. Silicone gel sheeting for preventing and treating hypertrophic and keloid scars. Cochrane Database Syst Rev 2013
- University Hospitals Dorset NHS Foundation Trust: Skin excision with local anaesthesia (patient leaflet)
- Care Quality Commission: Surgical procedures (scope of registration)
This article is general information about keloid scars and their surgical treatment and is not medical advice. Suitability for excision can only be decided after an in-person assessment. Keloids can recur after any treatment, and no result can be guaranteed. If a scar or lump is hot, swollen, discharging, bleeding or changing rapidly, seek medical advice promptly. Prices are indicative London market ranges for 2026 and are confirmed in writing after assessment.